Alirocumab: Classification, History, Mechanism of Action, Safety and Pharmacovigilance
Alirocumab is a fully human IgG1 monoclonal antibody directed against proprotein convertase subtilisin/kexin type 9 (PCSK9). It binds circulating PCSK9 and prevents PCSK9-mediated degradation of hepatic low-density lipoprotein receptors. The intended pharmacological consequence is to increase LDL-receptor availability and reduce circulating LDL cholesterol. These features provide the scientific starting point for pharmacovigilance: they identify plausible event phenotypes, relevant competing explanations and the exposure details that must remain traceable.
The target alone is not a safety profile. The underlying disease, prior and concomitant treatment, route of administration, patient susceptibility and duration of biological effect can each alter the meaning of a reported event. A defensible assessment therefore starts with mechanism and then tests that hypothesis against chronology, phenotype, objective evidence and alternatives.
- Alirocumab: Classification, History, Mechanism of Action, Safety and Pharmacovigilance
- Purpose and Clinical Context
- Multidimensional Classification
- Molecular Mechanism and Safety Reasoning
- Development and Regulatory History
- Clinical Safety Architecture
- Safety Domains and Targeted Follow-up
- Case Reconstruction and Differential Diagnosis
- Signal Detection and Aggregate Review
- Benefit-Risk Interpretation
- Practical Pharmacovigilance Implementation
- Potential Failure Modes
- Inspection and Governance Perspective
- Practical QPPV Checklist
- Key Takeaways
- References
- Regulatory Note
Purpose and Clinical Context
The clinical context is authorised lipid-lowering treatment in hypercholesterolaemia and mixed dyslipidaemia, with cardiovascular-risk reduction in defined populations according to regional product information. LDL lowering modifies risk; it does not erase pre-existing atherosclerotic disease or inherited cardiovascular susceptibility. Cardiovascular events therefore require contextual assessment rather than automatic classification as treatment failure.
For pharmacovigilance, the active-substance name is only the first level of identification. The record should preserve the exact product and presentation, route, dose, administration date, treatment phase and batch where available. This permits clinically meaningful case reconstruction and, where relevant, links an adverse event to product-quality or administration information rather than treating every report as a purely pharmacological effect.
Multidimensional Classification
| Axis | Alirocumab | Pharmacovigilance significance |
|---|---|---|
| Molecular format | fully human IgG1 monoclonal antibody | Establishes a biological product with product-specific quality and immunogenicity considerations |
| Target | proprotein convertase subtilisin/kexin type 9 (PCSK9) | Provides the mechanistic anchor for event assessment |
| Functional action | binds circulating PCSK9 and prevents PCSK9-mediated degradation of hepatic low-density lipoprotein receptors | Defines the biological perturbation created by treatment |
| Intended effect | increase LDL-receptor availability and reduce circulating LDL cholesterol | Connects mechanism with the expected clinical benefit |
| Route | subcutaneous injection using a pre-filled presentation | Determines administration chronology, handling and acute-reaction questions |
| Clinical context | authorised lipid-lowering treatment in hypercholesterolaemia and mixed dyslipidaemia, with cardiovascular-risk reduction in defined populations according to regional product information | Establishes background disease risk, co-treatment and the benefit population |
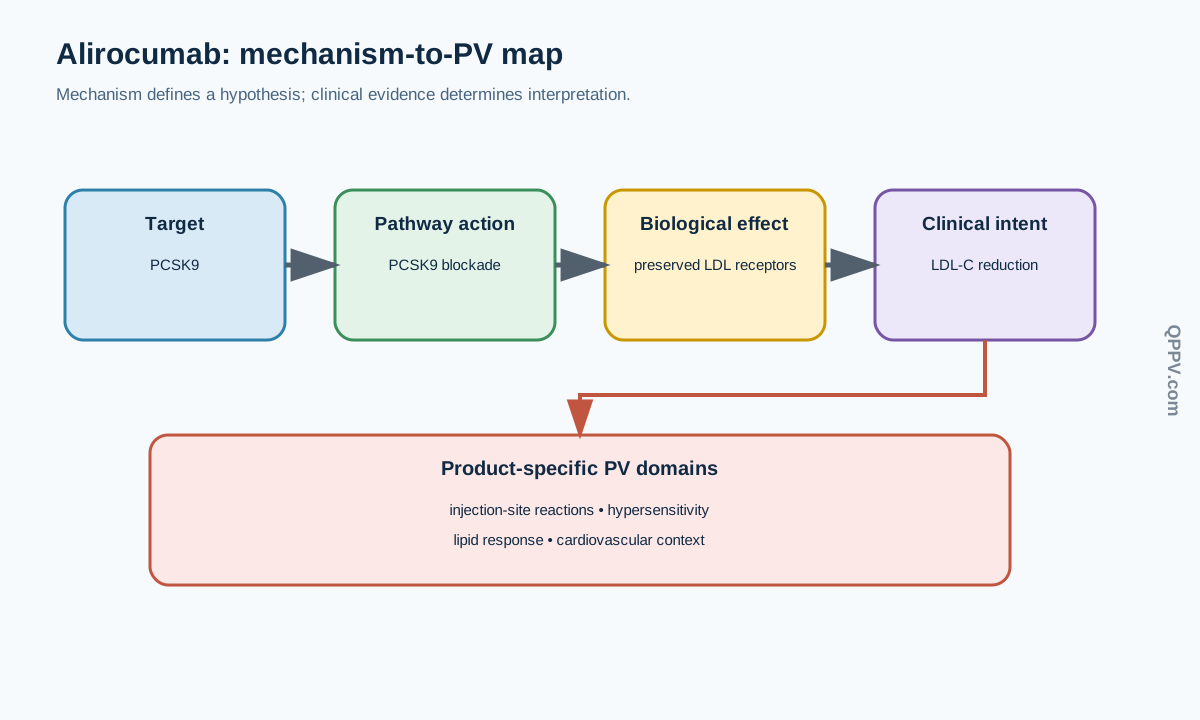
Figure 1. The target and pathway define a safety hypothesis; the patient, treatment context and observed phenotype determine whether that hypothesis is supported.
Molecular Mechanism and Safety Reasoning
Alirocumab binds circulating PCSK9 and prevents PCSK9-mediated degradation of hepatic low-density lipoprotein receptors. Its intended effect is to increase LDL-receptor availability and reduce circulating LDL cholesterol. A mechanism-led assessment can therefore proceed in four steps: identify the biological function being changed; define the tissues or physiological processes that may be affected; specify event phenotypes that would support the hypothesis; and identify observations that would weaken it or favour another cause.
For Alirocumab, important surveillance domains include injection-site reactions, pruritus and other hypersensitivity reactions, including rare serious hypersensitivity; apparent inadequate lipid response; cardiovascular events occurring despite therapy; and biological-product traceability. These domains are not interchangeable. They require different follow-up questions, case definitions and aggregate analyses. Combining them under a broad label such as “immune-related” or “treatment-related” would obscure clinically useful distinctions.
Mechanistic plausibility should be recorded as a reasoned hypothesis rather than a causal shortcut. It strengthens an assessment when the chronology, phenotype and objective evidence fit. It should not override contradictory timing, absent confirmation or a stronger competing explanation.
Development and Regulatory History
Alirocumab received EU marketing authorisation in 2015. Its development established PCSK9 inhibition as a biological strategy for lowering LDL cholesterol in patients whose residual lipid burden remains clinically important despite diet and other lipid-lowering measures.
Regulatory history matters because authorised populations, warnings and risk-minimisation measures can change as evidence accumulates. Current case processing and benefit-risk evaluation should use applicable current regional product information. Historical product information remains relevant when reconstructing what was authorised or listed at the time of a past exposure, but it should not be treated as the current regulatory position.
Current EMA product information describes alirocumab as a fully human IgG1 antibody to PCSK9 and includes biological traceability language requiring clear recording of product name and batch number.
Clinical Safety Architecture
Alirocumab safety is best understood through three interacting layers. The first is direct pharmacology arising from proprotein convertase subtilisin/kexin type 9 (PCSK9). The second is host susceptibility, including disease severity, organ reserve, infection history, immune status and relevant comorbidity. The third is the treatment environment: prior therapy, concomitant medicines, procedures, administration conditions and treatment phase.
This separation prevents a common attribution error. An event that occurs after exposure may be compatible with treatment, disease, co-therapy or an unrelated condition. Temporal association is one piece of evidence; it is not the conclusion.
Safety Domains and Targeted Follow-up
For Alirocumab, priority surveillance includes injection-site reactions, pruritus and other hypersensitivity reactions, including rare serious hypersensitivity; apparent inadequate lipid response; cardiovascular events occurring despite therapy; and biological-product traceability. Follow-up should obtain information capable of changing seriousness, causality, expectedness, traceability or signal interpretation rather than merely increasing the volume of case data.
| Clinical question | Information that can change assessment |
|---|---|
| Exposure and administration | Exact product, presentation, batch, dose, route, date, treatment phase, administration setting and interruptions |
| Mechanism-related event | Onset, phenotype, objective findings, severity, management, outcome and evidence linking the event to proprotein convertase subtilisin/kexin type 9 (PCSK9) biology |
| Host susceptibility | Baseline disease activity, comorbidity, organ function, infection or immune history and relevant prior therapy |
| Concomitant treatment | Complete regimen, recent changes, procedures and medicines capable of producing the same event |
| Product-quality question | Storage, preparation, device or infusion details, batch, complaint information and whether related cases exist |
| Product-specific follow-up | baseline and serial LDL-C, adherence, concomitant lipid-lowering treatment, injection timing and site, hypersensitivity phenotype, cardiovascular history, objective confirmation of cardiovascular events and outcome |
A targeted questionnaire or structured follow-up workflow can improve consistency, but the tool is not the endpoint. The quality question is whether clinically important answers were obtained when feasible, medically reviewed and incorporated into the narrative and assessment.
Case Reconstruction and Differential Diagnosis
A strong assessment reconstructs the sequence from treatment intent to outcome. Establish why Alirocumab was used and the clinical state before treatment. Then document exposure chronology, event onset and evolution, objective findings, management and outcome. Only after that chronology is stable should causality be weighed.
Important alternatives include underlying atherosclerotic cardiovascular disease, familial hypercholesterolaemia, non-adherence, changes in statin or other lipid-lowering therapy, intercurrent illness and laboratory variability. Their presence does not automatically exclude a treatment contribution. Conversely, the fact that an event is described in product information does not automatically establish causality in an individual case.
Dechallenge can be informative when improvement follows interruption, but its interpretation may be confounded by rescue treatment, co-medication changes or natural disease fluctuation. Rechallenge can add evidence when it occurs in routine care, but should not be manufactured as a pharmacovigilance experiment when clinically inappropriate.
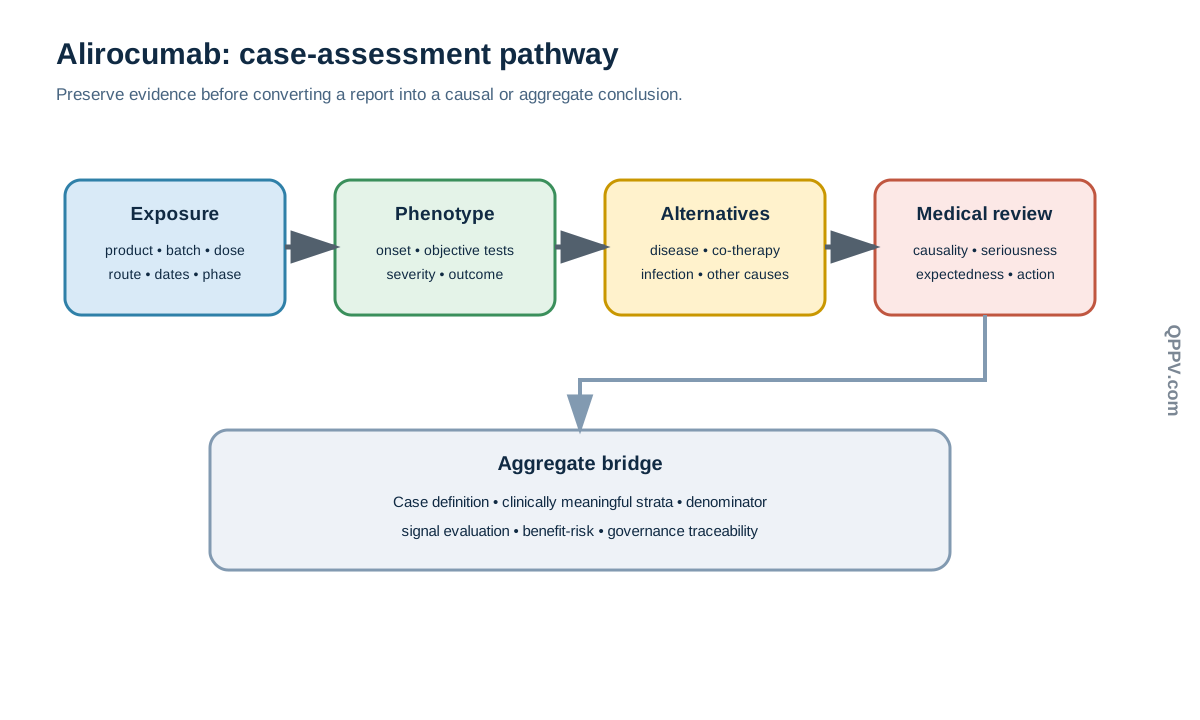
Figure 2. Exposure, phenotype and competing explanations are evaluated before a medical conclusion is carried into signal detection and aggregate benefit-risk review.
Signal Detection and Aggregate Review
Signal detection should preserve strata that can change event frequency or meaning. Depending on the product, useful dimensions include indication, biomarker-defined population, disease severity, treatment line, treatment phase, route, combination regimen, age, relevant comorbidity, prior therapy, region and product presentation.
Preferred-term counts are only a starting point. Several terms may describe one syndrome, while a single term may contain multiple mechanisms. For Alirocumab, medical review should therefore use clinically defensible event groupings and document the case definition applied.
A signal is a hypothesis requiring evaluation. Aggregate review should compare the observed pattern with background disease, known class effects, concomitant medicines, reporting stimulation, changes in clinical practice and product-quality information. Where exposure denominators are uncertain, the limitation should be stated rather than hidden behind a precise-looking rate.
Benefit-Risk Interpretation
Benefit-risk evaluation should preserve the population and treatment context in which the safety evidence arose. The relevant question is not whether adverse events exist, but whether the evolving pattern of benefit and risk remains acceptable for the authorised population under the applicable conditions of use.
For Alirocumab, periodic review should therefore connect event severity and preventability with treatment exposure, patient selection, disease burden, co-treatment and the effectiveness of applicable risk-minimisation measures. Changes in clinical practice can alter both the numerator of reports and the exposed population, so apparent trends require clinical interpretation.
Practical Pharmacovigilance Implementation
The operational system should make scientifically relevant information easy to capture, retrieve and analyse. For Alirocumab, this means preserving exact exposure details while ensuring that follow-up is driven by the event phenotype rather than by a generic biological-medicine checklist.
Recommended operational controls include structured capture of indication and treatment phase; exact product and batch where available; event-specific baseline and serial findings; documented competing causes; reconciliation with quality complaints and medical-information contacts; and aggregate outputs that retain clinically important subgroups. These are recommended system controls unless a specific legal, regulatory or procedural requirement makes a particular element mandatory.
Potential Failure Modes
The following are illustrative failure modes, not published inspection findings:
- A case is coded from a symptom without the objective findings needed to distinguish disease from treatment effect.
- The treatment regimen is collapsed into one exposure field, so co-treatment toxicity cannot be assessed.
- A known labelled event is accepted as causal without examining timing or competing explanations.
- Product presentation or batch information is omitted when a quality or administration issue is plausible.
- A treatment interruption is treated as complete dechallenge despite persistent biological activity.
- Aggregate review pools clinically different populations and masks a subgroup-specific pattern.
- Follow-up is sent but returned information is not incorporated into the medical assessment.
- Historical product information is used as though it represented the current regulatory position.
For Alirocumab, an additional product-specific weakness is failure to capture baseline and serial LDL-C, adherence, concomitant lipid-lowering treatment, injection timing and site, hypersensitivity phenotype, cardiovascular history, objective confirmation of cardiovascular events and outcome. That omission can materially change causality, signal interpretation or evaluation of risk minimisation.
Inspection and Governance Perspective
An inspection of Alirocumab pharmacovigilance would not stop at whether procedures exist. The relevant evidence is whether the system consistently converts source information into usable case narratives, medically reasoned assessments, appropriate follow-up, signal evaluations and documented benefit-risk decisions.
Evidence can include case-processing guidance, targeted follow-up tools, medical-review criteria, signal-detection outputs, periodic reports, reconciliation records, product and batch dictionaries, quality-complaint interfaces and governance records. The effectiveness question is whether these controls work together, whether weaknesses become visible, and whether corrective actions address the underlying process rather than only the individual case.
Practical QPPV Checklist
- Confirm the active substance, authorised clinical context and applicable current product information.
- Preserve product, presentation, batch, dose, route, dates and treatment phase.
- Reconstruct the phenotype with objective findings, severity, management and outcome.
- Compare the event with the mechanism-led hypothesis and with underlying atherosclerotic cardiovascular disease, familial hypercholesterolaemia, non-adherence, changes in statin or other lipid-lowering therapy, intercurrent illness and laboratory variability.
- Assess dechallenge and any real-world rechallenge without forcing a binary conclusion.
- Obtain targeted follow-up: baseline and serial LDL-C, adherence, concomitant lipid-lowering treatment, injection timing and site, hypersensitivity phenotype, cardiovascular history, objective confirmation of cardiovascular events and outcome.
- Stratify aggregate review by variables that materially alter event meaning.
- Link safety cases with quality, medical-information and other relevant system interfaces.
- Record uncertainty explicitly and explain its effect on the medical conclusion.
- Maintain traceability from source information through assessment to regulatory action.
Key Takeaways
Alirocumab is a fully human IgG1 monoclonal antibody directed against proprotein convertase subtilisin/kexin type 9 (PCSK9). Its mechanism provides a scientific framework for pharmacovigilance, but not a shortcut to causality. Reliable assessment depends on exact exposure, clinically meaningful phenotype, objective evidence, alternatives, treatment context and product traceability.
The practical objective is to preserve the distinctions that matter from intake through follow-up, medical review, signal detection, periodic benefit-risk evaluation and governance. This does not eliminate uncertainty; it makes uncertainty traceable and scientifically interpretable.
References
- European Medicines Agency: Alirocumab EPAR and current product information.
- U.S. National Library of Medicine DailyMed: Alirocumab labelling search.
- European Medicines Agency: Good pharmacovigilance practices.
- ICH E2C(R2): Periodic benefit-risk evaluation report.
- ICH E2A: Clinical safety data management.
Regulatory Note
This article is an educational pharmacovigilance reference, not a substitute for current local product information, clinical judgment or applicable legislation. Authorised indications, contraindications, monitoring, reporting obligations and risk-minimisation measures can differ by jurisdiction and can change over time. Current regulator-approved product information and validated local procedures govern case handling.