Evinacumab: Classification, History, Mechanism of Action, Safety and Pharmacovigilance
- Evinacumab: Classification, History, Mechanism of Action, Safety and Pharmacovigilance
- Multidimensional classification
- From classification to a safety hypothesis
- Development and regulatory context
- Clinical safety architecture
- Follow-up that changes the assessment
- Case assessment
- Causality, signal detection and benefit-risk
- Risk-management controls
- Common failure modes
- Practical QPPV checklist
- Key Takeaways
- References
- Regulatory Note
Evinacumab is a fully human IgG4 monoclonal antibody that binds angiopoietin-like protein 3 (ANGPTL3), a regulator of lipid metabolism. By inhibiting ANGPTL3, it can lower atherogenic lipoproteins through mechanisms that are not dependent solely on functional LDL receptors. It is used as an adjunct to diet and other lipid-lowering treatment in selected patients with homozygous familial hypercholesterolaemia. Pharmacovigilance must preserve the severe inherited disease context, concomitant treatment, apheresis, infusion chronology and cardiovascular outcomes.
The pharmacovigilance question is broader than whether an event appears in a label. A useful assessment asks what biological function changed, when exposure occurred, what other therapies were present, which disease processes could produce the same finding and whether the event persisted after treatment was held.
Multidimensional classification
| Axis | Evinacumab | PV significance |
|---|---|---|
| Molecular format | Fully human IgG4 monoclonal antibody | A biological product with product-specific quality and immunogenicity considerations |
| Target | Angiopoietin-like protein 3 (ANGPTL3) | Identifies a regulator of lipoprotein lipase and endothelial lipase activity |
| Functional class | ANGPTL3-directed lipid-lowering therapy | Explains LDL-receptor-independent lipid lowering in a genetically defined population |
| Route | Intravenous infusion at a repeated monthly interval | Creates infusion-rate, observation, batch and concomitant-treatment traceability requirements |
| Clinical context | Adjunctive treatment for selected patients with homozygous familial hypercholesterolaemia | Baseline LDL burden, atherosclerotic disease, apheresis and other medicines affect interpretation |
| Treatment intent | Reduction of atherogenic lipoprotein exposure over time | A cardiovascular event cannot be interpreted without the underlying disease and exposure history |
From classification to a safety hypothesis
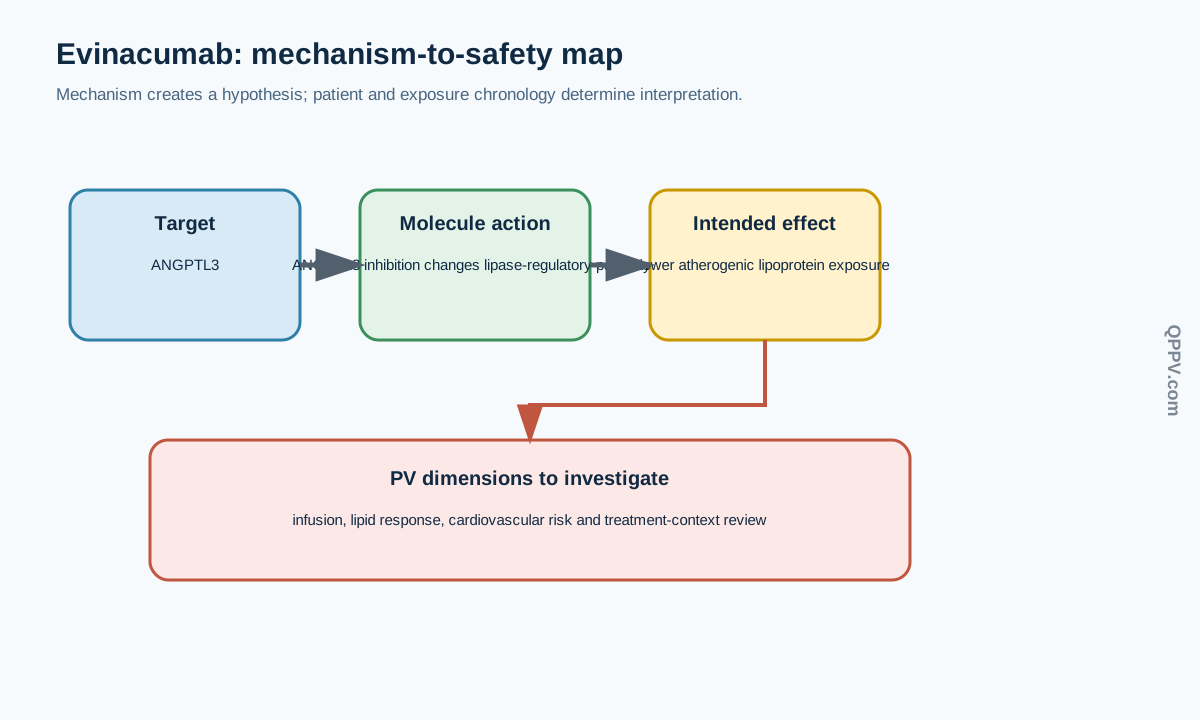
The target identifies the pathway being modified. The antibody format identifies a biological product with critical quality attributes that can influence exposure, immunogenicity and product-specific safety questions. The route creates a defined chronology with opportunities for administration reactions, handling errors and incomplete traceability.
For Evinacumab, the principal mechanism-led safety hypothesis is that inhibits ANGPTL3-mediated regulation of lipoprotein lipase and endothelial lipase pathways. The intended clinical effect is reduction of atherogenic lipoprotein levels in the authorised adjunctive treatment setting. The relevant pharmacovigilance concern is not simply an “immune effect”; it is the interaction between target biology, host susceptibility, concurrent treatment, disease activity and persistence of pharmacodynamic activity.
The mechanism therefore directs attention to infusion-related or hypersensitivity reactions, nasopharyngitis, dizziness or other reported symptoms requiring assessment, laboratory changes, treatment interruption, immunogenicity and cardiovascular events in the context of severe inherited lipid risk. It does not establish causality. A reported event must still be assessed against timing, objective findings, dechallenge, rechallenge when it occurs in routine care, alternative explanations and outcome.
Development and regulatory context
The safety record should preserve the familial hypercholesterolaemia genotype or clinical diagnosis, baseline and serial lipid values, apheresis schedule, statin or other lipid-lowering treatment, infusion date, cardiovascular history and treatment adherence. A myocardial infarction or vascular event may occur despite treatment because inherited disease risk is high and risk reduction is not equivalent to risk elimination.
The history of a biological medicine is also a history of changing clinical use. New indications, new age groups, new devices, switching patterns, combination regimens and longer exposure create new denominators and new opportunities for signal detection. A periodic review should distinguish evidence generated in the original development programme from evidence arising after broader clinical use.
A case that records only the substance name may be insufficient for investigation. Conversely, the presence of a plausible pathway does not mean that every infection, laboratory abnormality, neurological symptom or disease flare is drug-related. The useful question is whether the phenotype, timing, objective evidence and alternatives fit the proposed mechanism better than competing explanations do.
Clinical safety architecture
Evinacumab safety is best understood through three interacting layers. The first is direct pharmacology: the biological function changed by angiopoietin-like protein 3 (ANGPTL3). The second is host susceptibility, including age, baseline organ function, disease severity, infection history, comorbidity and prior treatment. The third is the treatment environment, including procedures, concomitant medicines, treatment line and the reason treatment was started.
The same outward symptom can arise from different layers. Fever may reflect infection, inflammation or an administration-related reaction. A laboratory abnormality may be pharmacodynamic, a manifestation of organ injury, a consequence of disease activity or an effect of another medicine. A new neurological, respiratory, gastrointestinal or musculoskeletal finding may represent treatment toxicity, the underlying disease or an unrelated acute illness. The narrative must preserve baseline status, serial findings and the complete regimen rather than assigning causality from the event term alone.
Follow-up that changes the assessment
| Event or question | High-value follow-up |
|---|---|
| Infusion or hypersensitivity reaction | dose, infusion rate, onset, vital signs, phenotype, treatment, observation period, batch and outcome |
| Cardiovascular event | baseline atherosclerotic disease, lipid values, apheresis, concomitant medicines, event confirmation, revascularisation, competing risk factors and outcome |
| Apparent inadequate lipid response | baseline and serial LDL or other lipid measurements, timing relative to infusion and apheresis, adherence, concomitant therapy, laboratory method and alternative explanations |
| Laboratory or systemic abnormality | baseline status, serial tests, renal or hepatic context, concomitant medicines, clinical phenotype, treatment and outcome |
| Suspected quality complaint or immunogenicity | product, presentation, batch, storage, preparation, administration, anti-drug-antibody information where available and co-exposed patients |
Each request should target information capable of changing seriousness, causality, expectedness, signal interpretation or traceability. “Follow-up requested” is not a quality measure by itself; the useful measure is whether the information was obtained, evaluated and incorporated into the case.
Case assessment
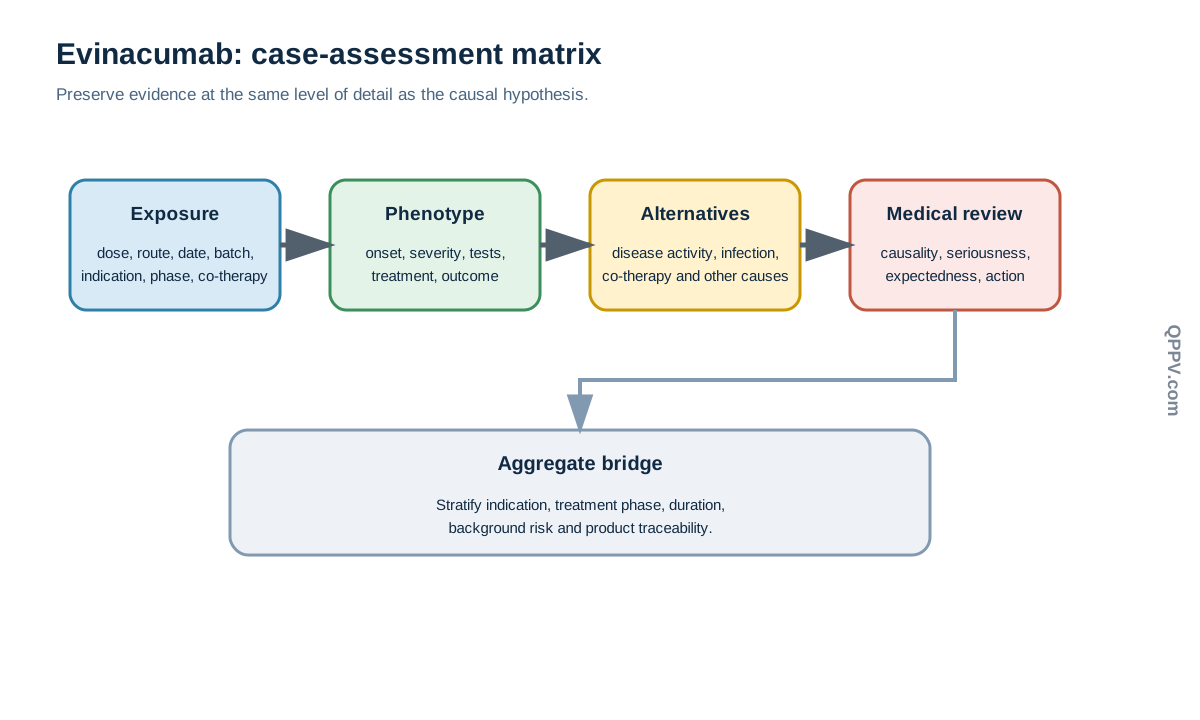
A strong assessment reconstructs a chain of events. Begin with why treatment was started and what outcome was intended. Establish exact exposure dates, dose, route, formulation, administration setting and batch, followed by concomitant medicines, recent procedures and prior biological therapies. Next describe onset, evolution, objective findings, treatment and outcome. Finally document alternative causes and the evidence for or against each one.
For Evinacumab, the most important differential set includes progression of familial hypercholesterolaemia, atherosclerotic cardiovascular disease, apheresis-related changes, concomitant lipid-lowering treatment, diabetes or hypertension and another acute cardiovascular or neurological illness. Reviewers should record evidence before applying broad labels such as pathway-related, immune-mediated, treatment failure or administration reaction. Temporal association is necessary but rarely sufficient. A plausible mechanism strengthens a hypothesis; a strong competing cause weakens it.
Dechallenge may be informative, but it is often confounded by rescue therapy, hospital care, changes in concomitant medicines or natural disease fluctuation. Rechallenge can provide evidence, but it may be clinically inappropriate and should never be treated as a routine diagnostic test. For a persistent biological effect, interruption does not necessarily mean immediate biological reversal.
Causality, signal detection and benefit-risk
Causality should be stated with calibrated language. A case may support a relationship, remain indeterminate or be more consistent with another cause. The reasoning should connect exposure, phenotype, timing, objective evidence, dechallenge, competing explanations and outcome.
Signal detection should preserve strata that can change event frequency or meaning: indication, disease severity, treatment line, monotherapy or combination therapy, duration, age, baseline organ function, prior treatment, region, treatment phase and product presentation. Preferred-term counts are only a starting point. Several terms may represent one syndrome, while one term may combine multiple mechanisms.
Before drawing a conclusion, align the case definition, medical review, laboratory or imaging confirmation, exposure denominator and outcome severity. Compare the observed pattern with background disease rates, known class effects, concomitant medicines, reporting stimulation, changes in clinical practice and product or batch information. A signal is a hypothesis requiring evaluation, not proof of a causal relationship.
Risk-management controls
An effective system should make scientifically relevant information easy to capture and retrieve. Important controls for Evinacumab include:
- structured fields for indication, treatment intent, treatment line and combination therapy;
- exact dose, route, administration date, formulation, presentation and batch;
- event-specific follow-up with baseline and serial findings;
- documented competing causes and explicit medical reasoning;
- reconciliation with quality complaints, medical-information contacts and distribution records;
- aggregate analyses stratified by population, regimen and treatment phase.
The controls should match the mechanism. For Evinacumab, that means ensuring that infusion-related or hypersensitivity reactions, nasopharyngitis, dizziness or other reported symptoms requiring assessment, laboratory changes, treatment interruption, immunogenicity and cardiovascular events in the context of severe inherited lipid risk are not collapsed into a single undifferentiated “immune-related” category. A mechanism-led review should identify the phenotype that would support the hypothesis, the evidence that would weaken it and the information required to resolve uncertainty.
Common failure modes
Coding a symptom without recording objective findings may make disease activity indistinguishable from treatment effect. Assessing a serious event without reviewing baseline disease, procedures or concomitant treatment leaves major alternatives unexplored. Treating interruption as complete dechallenge may ignore persistent pharmacodynamic activity. Omitting presentation, batch, storage or administration details can make a quality investigation impossible.
For Evinacumab, another recurrent error is to pool distinct clinical contexts. The safety record should preserve the familial hypercholesterolaemia genotype or clinical diagnosis, baseline and serial lipid values, apheresis schedule, statin or other lipid-lowering treatment, infusion date, cardiovascular history and treatment adherence. A myocardial infarction or vascular event may occur despite treatment because inherited disease risk is high and risk reduction is not equivalent to risk elimination. A periodic review should therefore state the population denominator, the exposure definition and the limitations of case completeness.
These are not merely documentation defects. They can change causality, signal strength, expectedness, traceability and regulatory decisions. During inspection, the important question is not whether a procedure exists, but whether it produces reliable evidence.
Practical QPPV checklist
- Confirm the active substance, indication, local authorisation and exact presentation.
- Reconstruct dose, route, dates, formulation, batch and administration setting.
- Describe the phenotype with objective findings, severity, treatment and outcome.
- Compare the event with the mechanism-led hypothesis and with progression of familial hypercholesterolaemia, atherosclerotic cardiovascular disease, apheresis-related changes, concomitant lipid-lowering treatment, diabetes or hypertension and another acute cardiovascular or neurological illness.
- Assess dechallenge and any routine-care rechallenge without manufacturing exposure.
- Request targeted follow-up that could change the medical conclusion.
- Stratify signal detection by indication, treatment phase, duration and relevant host risk.
- Link individual cases to quality, medical-information and aggregate processes.
- Record uncertainty explicitly and explain its impact on benefit-risk.
- Preserve source-to-decision traceability.
Key Takeaways
Evinacumab pharmacovigilance is mechanism-led but never mechanism-only. angiopoietin-like protein 3 (ANGPTL3) provides the biological anchor, while reliable interpretation requires the patient’s disease, susceptibility, co-medications, treatment chronology, objective findings and product identity.
In practice, preserve the authorised clinical context, follow up according to the event, document competing explanations, stratify aggregate analyses and maintain traceability from source information to regulatory action. This approach does not eliminate uncertainty. It makes uncertainty visible, reasoned and manageable.
References
- European Medicines Agency: Evinacumab EPAR and product information.
- U.S. National Library of Medicine: Evinacumab prescribing information.
- EMA: Good pharmacovigilance practices.
- ICH E2C(R2): Periodic benefit-risk evaluation report.
- ICH E2A: Clinical safety data management.
Regulatory Note
This article is an educational pharmacovigilance analysis, not a substitute for current local product information, clinical judgment or applicable legislation. Authorised indications, contraindications, monitoring, reporting duties and risk-minimisation measures vary by jurisdiction and may change. The current regulator-approved product information and validated safety procedures govern case handling.