How to Write a PBRER or PSUR for a Biological Medicinal Product
A Periodic Benefit–Risk Evaluation Report (PBRER) is the International Council for Harmonisation (ICH) format for periodically reassessing a medicinal product's benefits and risks. In the European Union (EU), the corresponding regulatory submission is the Periodic Safety Update Report (PSUR). The EU PSUR uses the ICH E2C(R2) content architecture with EU-specific legal, procedural and regional requirements.
The report is not an interval inventory. It is a periodically reconstructed evidence model. Each section performs a defined transformation: it identifies the product and reporting boundary, introduces relevant evidence, tests whether cumulative knowledge has changed, characterises benefits and risks, and converts the integrated conclusion into action. A section is adequate only when the reader can trace its conclusion to compatible evidence elsewhere in the report.
Biological medicines require several nested exposure identities. The active substance describes the biologically active material; the authorised product identifies a particular medicine; the brand, formulation, route and device define how that product is supplied and administered; and the batch connects exposure to a manufacturing unit. The analytical level must match the question. A target-mediated infection risk may apply across a pharmacological class, while incomplete delivery may concern one injector lot.
This article applies the biological foundations explained in Biological Medicinal Products: Classification, Development and Pharmacovigilance and complements QPPV.com's guides to PSUR safety evaluation, biological RMPs, biological signal management and biological ICSR management.
Table of Contents
- Regulatory framework and reporting boundaries
- Continuing worked dossier
- The repeated writing method
- Title page
- Executive summary
- Section 1: Introduction
- Section 2: Worldwide Marketing Approval Status
- Section 3: Actions Taken in the Reporting Interval for Safety Reasons
- Section 4: Changes to Reference Safety Information
- Section 5: Estimated Exposure and Use Patterns
- 5.1 Cumulative subject exposure in clinical trials
- 5.2 Cumulative and interval patient exposure from marketing experience
- Section 6: Data in Summary Tabulations
- 6.1 Reference information
- 6.2 Cumulative serious adverse events from clinical trials
- 6.3 Cumulative and interval post-marketing tabulations
- Section 7: Summaries of Significant Findings from Clinical Trials
- 7.1 Completed clinical trials
- 7.2 Ongoing clinical trials
- 7.3 Long-term follow-up
- 7.4 Other therapeutic use
- 7.5 New safety data related to fixed combinations
- Section 8: Findings from Non-Interventional Studies
- Section 9: Information from Other Clinical Trials and Sources
- Section 10: Non-Clinical Data
- Section 11: Literature
- Section 12: Other Periodic Reports
- Section 13: Lack of Efficacy in Controlled Clinical Trials
- Section 14: Late-Breaking Information
- Section 15: Overview of Signals
- Section 16: Signal and Risk Evaluation
- 16.1 Summary of safety concerns
- 16.2 Signal evaluation
- 16.3 Evaluation of risks and new information
- 16.4 Characterisation of risks
- 16.4.1 Define the risk and attribution level
- 16.4.2 Frequency, numerator and denominator
- 16.4.3 Absolute and relative risk
- 16.4.4 Seriousness, severity and patient impact
- 16.4.5 Public-health impact
- 16.4.6 Patient and disease risk factors
- 16.4.7 Dose, route, duration and risk window
- 16.4.8 Preventability and detectability
- 16.4.9 Reversibility and clinical course
- 16.4.10 Mechanism and biological plausibility
- 16.4.11 Evidence strength, uncertainty and conflict
- 16.4.12 Missing information
- 16.5 Effectiveness of risk minimisation
- Section 17: Benefit Evaluation
- 17.1 Important baseline efficacy and effectiveness information
- 17.2 Newly identified information on efficacy and effectiveness
- 17.3 Characterisation of benefits
- Section 18: Integrated Benefit–Risk Analysis
- 18.1 Benefit–risk context: medical need and alternatives
- 18.2 Benefit–risk analysis evaluation
- Section 19: Conclusions and Actions
- Section 20: Appendices
- Authoring workflow and governance
- Section-to-source planning matrix
- Cross-section reconciliation matrix
- Medical-review questions
- Final consistency test
- Practical authoring sequence
- Common article-wide failure modes
- Key Takeaways
- References
- Regulatory Note
Regulatory framework and reporting boundaries
ICH E2C(R2) defines the PBRER structure and purpose. EU GVP Module VII defines the EU PSUR system, while the current explanatory note and PSUSA material clarify EU assessment practice. GVP Product- or Population-Specific Considerations II addresses biological-specific pharmacovigilance. These sources should be read together, but legal requirements, regulatory guidance and recommended authoring practice must remain distinguishable.
The data lock point (DLP) is the date through which the main reporting dataset is included. The reporting interval begins after the preceding DLP and ends at the current DLP. Cumulative data extend from the applicable origin—commonly the international birth date for post-authorisation presentation—through the current DLP. The DLP controls reproducibility; it does not terminate scientific awareness. Material post-DLP evidence is handled in Section 14.
The reference safety information (RSI) is the stated baseline used for the periodic evaluation. The writer records its title, version and effective date. Changing the RSI during authoring without controlled explanation can change classifications and invalidate comparisons.
Continuing worked dossier
The fictional product mAb-X is an immunomodulatory monoclonal antibody authorised for severe Disease A and moderate Disease B. It is supplied as an intravenous infusion and as a subcutaneous pre-filled injector. Biosimilars are marketed by other holders. During the interval:
- a delayed-hypersensitivity signal is evaluated;
- injector lot L17 produces incomplete-dose complaints;
- one cohort reports increased anti-drug-antibody positivity after switching;
- serious-infection rates remain stable across trials and registries;
- a manufacturing site transfer produces a small glycan shift within the approved comparability range;
- a new indication, Disease B, has shorter follow-up and lower baseline severity.
No numerical value in the example represents a real product. Where illustrative numbers appear, they demonstrate method rather than expected results.
The repeated writing method
For every section, use the same six questions:
| Question | Authoring consequence |
|---|---|
| What regulatory problem does the section solve? | State its purpose before presenting data |
| What evidence belongs here? | Name sources, interval/cumulative boundary and limitations |
| What changes for a biological? | Select class, substance, product, batch, formulation, route or device level |
| What reasoning is required? | Explain comparison, uncertainty and alternative interpretations |
| What does mAb-X demonstrate? | Apply the method to one continuing dossier |
| What must reconcile elsewhere? | Identify dependent tables, evaluations and actions |
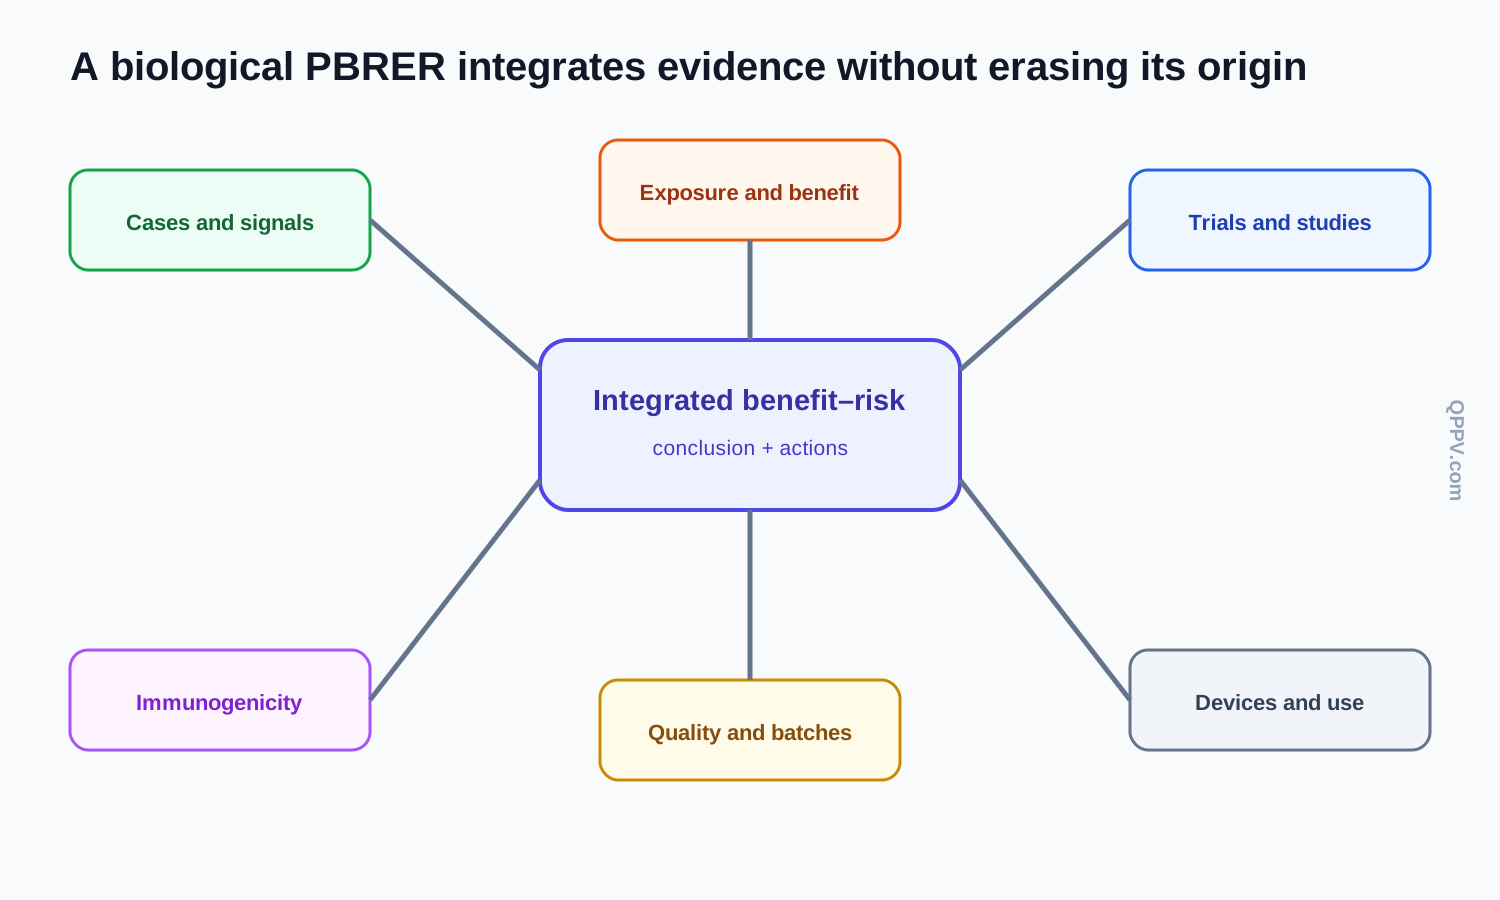
Figure 1. The PBRER reconstructs one evidence model from safety, exposure, benefit, quality, immunogenicity and product-identity sources. Integration does not erase the limitations of each source.
Title page
Purpose and required content
The title page fixes document identity: active substance, included proprietary products, reporting interval, DLP, report sequence, international birth date where applicable, marketing authorisation holder and confidentiality status.
Biological-specific reasoning
List included formulations, routes and presentations when scope could otherwise be misunderstood. A title page that states only the active substance can imply inclusion of products or biosimilars outside the holder's dataset.
Worked example and reconciliation
For mAb-X, name both company presentations and explicitly state that external biosimilar evidence may be discussed but their exposure is not included in company denominators. Reconcile all dates and product names with Sections 1, 2, 5 and the appendices.
Common error and output
Do not use a global brand where different territories have different products. The output is an unambiguous document boundary against which every later inclusion can be tested.
Executive summary
Purpose and inputs
The executive summary allows an assessor to understand what changed, why it matters and what is proposed. Draft it after Sections 15–19 are stable. Include scope, interval exposure, important actions, signal status, important risk changes, benefit changes, integrated benefit–risk conclusion and proposed actions.
Biological-specific reasoning
Mention manufacturing, batch, immunogenicity or device information only when it materially affects interpretation. Their mere existence is not a safety conclusion.
Worked example
The mAb-X summary distinguishes delayed hypersensitivity, which may affect product information, from the L17 injector issue, which supports presentation-specific corrective action. Stable infection evidence and unresolved switching/immunogenicity uncertainty are both stated.
Common error and reconciliation
Avoid “no new safety concern” when a signal remains under evaluation. Every summary statement must match Sections 3, 4, 15, 16, 18 and 19.
Section 1: Introduction
Regulatory purpose
Section 1 identifies what report is being evaluated. It is not a general disease introduction. State international birth date, interval, DLP, active substance, product scope, indications, populations, doses, formulations and routes. Add a concise mechanism only where it explains later benefits or risks.
Evidence inputs
Use authorised product information, approval records, the reporting schedule, current RSI and controlled product dictionaries. Confirm whether combinations, partner products, territories, presentations or legacy formulations are included.
Biological-specific reasoning
Explain the relationship between active substance, reference product, company biosimilar, external biosimilars, device constituents and presentations. If the intravenous and subcutaneous forms share the same protein but differ in excipients and administration, later analyses must preserve that distinction.
mAb-X example
“mAb-X inhibits immune target T. This PBRER covers the holder's intravenous vial and subcutaneous injector for Disease A and Disease B. External biosimilar evidence is considered where relevant but is not treated as company exposure.”
This framing anticipates target-mediated infection risk, route-specific reactions and device-specific underdelivery.
Common errors, reconciliation and output
Do not copy a mechanism paragraph while omitting actual scope. Reconcile with Sections 2, 5 and 20. The output is the formal interpretive frame for the report.
Section 2: Worldwide Marketing Approval Status
Regulatory purpose
Section 2 locates the product across regulatory systems. It shows where and for what uses evidence and exposure could arise.
Evidence inputs
Use regulatory databases and controlled approval records. Capture first approval, countries or regions, indications, age groups, route, strength, formulation, presentation, prescription status and significant interval changes.
Biological-specific reasoning
A biological may have different brands, devices, strengths or authorised indications across territories. Interchangeability and substitution positions are jurisdiction-specific and should not be generalised from biosimilar authorisation.
Presentation method
A decision-useful table is preferable to a country list:
| Territory | Exact product | Presentation | Indication/population | Interval change |
|---|---|---|---|---|
| A | mAb-X IV | Vial/infusion | Disease A, adults | None |
| B | mAb-X SC | Pre-filled injector | Disease A and B | Disease B added |
| C | Partner brand | Vial/infusion | Disease A | Licence transferred |
Reasoning and worked example
Disease B exposure cannot precede its approval date in Territory B without explanation such as trial or off-label use. A device complaint cannot be assigned to territories where only the vial is marketed.
Common errors and reconciliation
Do not state “approved worldwide” when presentations differ. Reconcile approval dates and status with Sections 3, 5, 7, 13 and 17. The output is the regulatory map needed to interpret exposure and action.
Section 3: Actions Taken in the Reporting Interval for Safety Reasons
Regulatory purpose
Section 3 records significant actions taken because of safety information. It permits the assessor to understand what was considered urgent or consequential before reading the detailed evaluation.
Evidence inputs
Collect regulator decisions, holder actions, study actions, ethics-committee decisions, data-monitoring recommendations, batch recalls, device field actions, restrictions, safety communications and changes to risk-minimisation activities. For each, record date, territory, trigger, product scope, action, rationale and status.
Biological-specific reasoning
Separate four propositions:
- a quality deviation occurred;
- patients were exposed;
- a clinical consequence was reported;
- a causal safety risk was established.
They may coexist, but one does not prove the next. A batch recall may be precautionary; a device correction may prevent underdosing without implying altered molecular potency.
mAb-X example
Injector lot L17 was subject to a field correction after incomplete-dose complaints. State affected countries, lot, presentation, start date, communication and replacement process. Section 16 evaluates clinical consequences; Section 16.5 evaluates effectiveness.
Common errors and reconciliation
Do not bury a recall in a quality appendix or describe it as proof of adverse reaction. Reconcile with Sections 4, 14–16, 19 and relevant appendices. The output is a traceable action chronology.
Section 4: Changes to Reference Safety Information
Regulatory purpose
Section 4 shows how the safety baseline changed during the interval and what evidence produced each change.
Evidence inputs
Use the RSI version history, change-control record, core safety committee decisions and regional product-information changes. Record old and new versions, approval/effective dates, changed topics and scientific basis.
Biological-specific reasoning
Potential topics include immunogenicity, infusion or injection reactions, infections, vaccination, traceability, storage, preparation, excipients, device use and pregnancy. A manufacturing change belongs here only if it changes safety information; otherwise it may be relevant in Sections 3, 10 or 16.
mAb-X example
Delayed hypersensitivity remains under evaluation and therefore is not yet added to the RSI. State this explicitly. The absence of a change does not mean absence of a signal. A device-use instruction changed after L17; distinguish instructions for use from core adverse-reaction wording.
Common errors, reconciliation and output
Do not list wording changes without their evidentiary basis or silently use a later RSI for the entire interval. Reconcile with Sections 6, 15, 16, 19 and the EU regional appendix. The output is a controlled map of how the reference baseline evolved.
Section 5: Estimated Exposure and Use Patterns
Exposure provides scale and distribution for interpreting benefits and risks. It is not automatically a valid denominator for spontaneous reports. The numerator and denominator must refer to compatible populations, products, periods and outcome-ascertainment systems before a rate is calculated.
5.1 Cumulative subject exposure in clinical trials
Purpose and inputs
Summarise cumulative trial exposure by indication, study phase, randomised treatment, dose, route, duration, age, sex and clinically relevant population. Use verified trial datasets rather than adding publication totals that may double-count participants.
Biological-specific reasoning
Include repeat courses, loading and maintenance schedules, route, formulation, treatment duration, pharmacokinetic sampling and immunogenicity testing where material. Long receptor occupancy or immune effects may justify follow-up categories extending beyond last dose.
Analytical method
Distinguish:
- number exposed at least once;
- person-time under treatment;
- duration categories;
- cumulative dose;
- exposure after formulation or manufacturing change;
- number with valid anti-drug-antibody samples.
Immunogenicity-tested participants are a selected denominator if sampling is incomplete. Never use them as though they represented all exposed participants without stating selection.
mAb-X example
Present Disease A IV, Disease A SC and Disease B SC separately. The new Disease B programme contributes less cumulative person-time; “no serious infection increase” therefore carries wider uncertainty than in Disease A.
Common errors and reconciliation
Avoid summing overlapping extension cohorts or comparing percentages with different follow-up. Reconcile with Sections 7, 13, 16 and 17. The output is the controlled trial-exposure context.
5.2 Cumulative and interval patient exposure from marketing experience
Purpose and inputs
Estimate cumulative and interval post-marketing exposure using sales, distribution, prescriptions, administrations, registry data or other justified sources. Describe data provenance, geographic coverage, conversion formula, assumptions and uncertainty.
Biological-specific reasoning
Stratify by exact product, route, presentation, indication, region and relevant manufacturing period when the safety question requires it. Keep external biosimilar exposure separate from the holder's denominator unless a valid shared analysis has been designed.
Converting units to exposure
If 100,000 syringes were distributed, the number of patients depends on dosing frequency, treatment duration, loading doses, wastage and adherence. A transparent calculation is:
[ ext{Estimated patient-years} = rac{ ext{usable doses distributed}} { ext{recommended doses per patient-year}} ]
The apparent precision of the result must not exceed the precision of its assumptions. Provide sensitivity analyses when dose intensity varies materially.
Use-pattern analysis
Describe age, sex, indication, dose, duration, off-label use, switching and geographic pattern where data allow. Separate verified administration from distribution. For hospital infusions, administration records may be stronger than sales; for self-injection, dispensed units do not prove injection.
mAb-X example
The rise in incomplete-dose reports is evaluated against SC injector units from the affected lot and period, not against total IV-plus-SC active-substance exposure. Delayed hypersensitivity may require both route-specific and product-wide exposure views.
Common errors and reconciliation
Do not calculate incidence by dividing spontaneous reports by sales-derived exposure. Reconcile totals with Sections 2, 6, 15, 16 and 18.
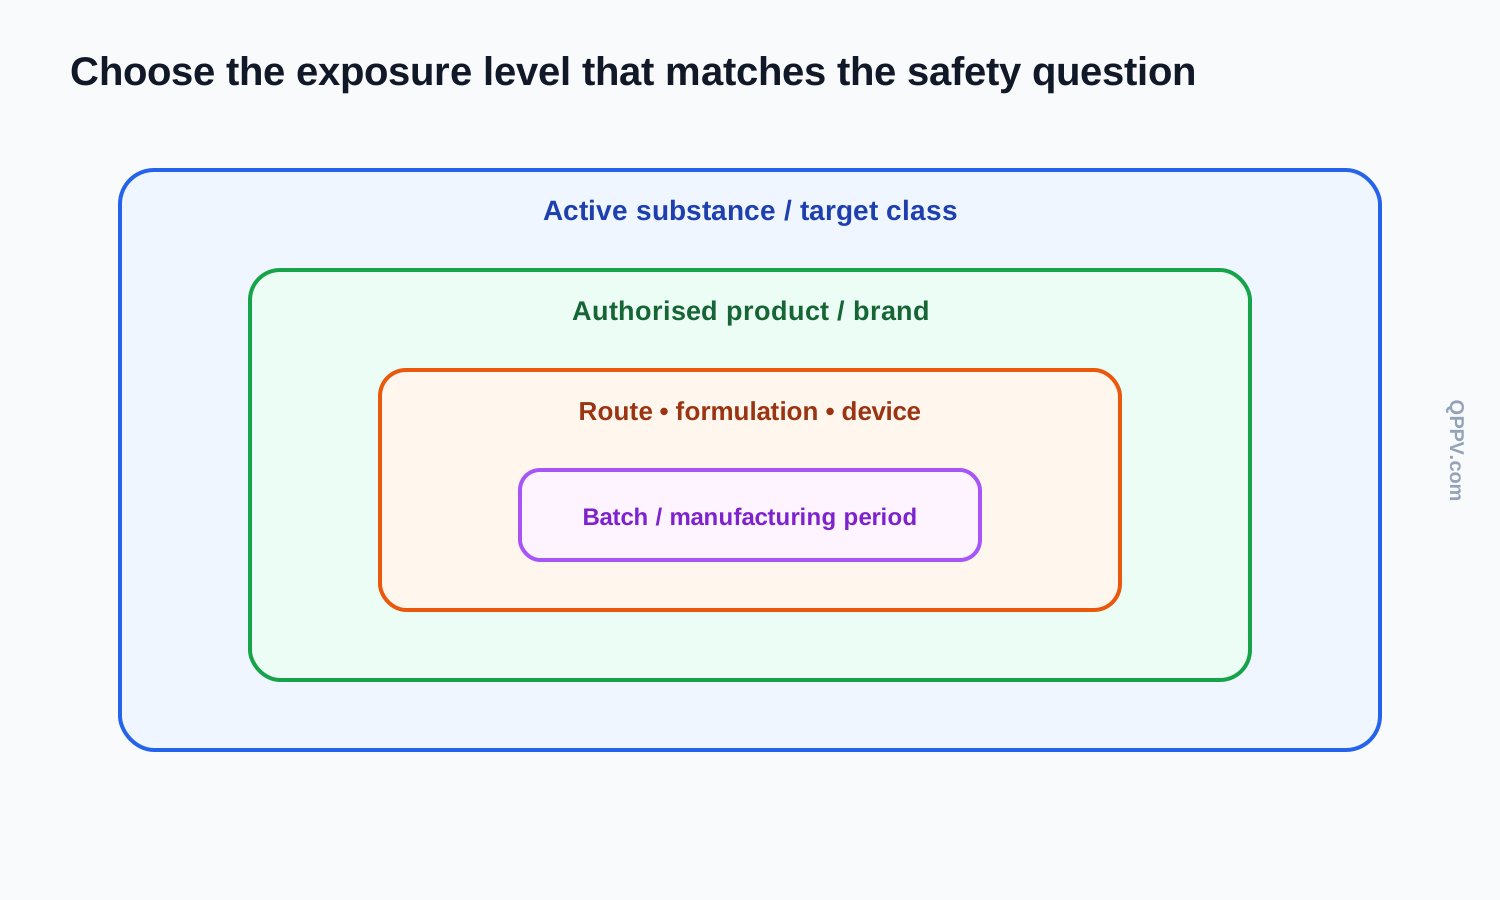
Figure 2. Exposure must be estimated at the level needed for the safety question. Broad aggregation supports substance-level interpretation; route, presentation, batch and manufacturing-period strata support specific hypotheses.
Section 6: Data in Summary Tabulations
Tabulations describe reported events and reactions in a consistent hierarchy. They are not risk evaluations. Their value depends on controlled coding, deduplication, case inclusion rules and transparent reference information.
6.1 Reference information
Purpose and inputs
State the Medical Dictionary for Regulatory Activities (MedDRA) version, coding conventions, RSI used for listedness or expectedness where applicable, database cut and case-inclusion rules.
Biological-specific reasoning
Explain how products were grouped and how unknown brand or batch was handled. Do not allocate unknown products proportionally or infer a brand from country unless source evidence supports it.
mAb-X example
Cases coded to the active substance include those with unknown presentation. A focused injector analysis includes only confirmed SC devices. This difference explains why totals in the focused analysis are smaller.
Common errors and reconciliation
Do not retroactively recode historical expectedness without explaining the method. Reconcile reference versions with Section 4 and table footnotes.
6.2 Cumulative serious adverse events from clinical trials
Purpose and analytical unit
Present cumulative serious adverse events from clinical trials in the required format. State whether counts are subjects, events or both. Preserve blinded integrity when required.
Biological-specific reasoning
Useful strata may include indication, route, dose, formulation, exposure duration, manufacturing version and anti-drug-antibody status, but only when the study design supports comparison. Post-baseline antibody status can be time-dependent and should not be treated as a simple baseline group.
mAb-X example
Serious infections are shown by randomised group and indication with person-time. An exploratory ADA-positive subgroup is labelled descriptive because testing times and treatment duration differ.
Common errors and reconciliation
Do not combine treatment-emergent events from incompatible study periods. Reconcile with Sections 5.1, 7, 13 and 16.
6.3 Cumulative and interval post-marketing tabulations
Purpose and inputs
Provide cumulative and interval adverse-reaction tabulations according to the format. Define spontaneous, solicited and study-derived inclusion and explain multiple reactions within cases.
Biological-specific reasoning
Report product-identification completeness alongside relevant focused analyses. A complaint without a clinical reaction is not converted into an adverse-reaction count, although linked complaint information may inform assessment.
mAb-X example
The main table reports delayed-hypersensitivity reaction terms. A separate evaluation identifies confirmed IV, confirmed SC and unknown route. L17 complaint counts are reconciled to the smaller subset with clinical consequences.
Common errors and reconciliation
Counts cannot establish frequency without compatible ascertainment and exposure. Reconcile with Sections 5.2, 15, 16 and complaint records.
Section 7: Summaries of Significant Findings from Clinical Trials
The section reports medically important new trial findings, not every table generated during the interval. For each subsection state study identifier, design, population, product/version, comparator, exposure, relevant result, limitation and implication.
7.1 Completed clinical trials
Purpose and inputs
Summarise completed trials with significant safety information. Use final or sufficiently mature analyses and explain whether results were prespecified or exploratory.
Biological-specific reasoning
Compare route, formulation, dose, device, immunogenicity and manufacturing version when scientifically justified. Explain assay methods and sampling schedules when antibody data influence interpretation.
mAb-X example
A completed SC trial shows similar overall safety to IV but more local injection reactions. Because administration route differs, this is a presentation-specific tolerability finding, not evidence of changed active-substance systemic risk.
Errors, reconciliation and output
Do not select only statistically notable findings without clinical context. Reconcile with Sections 5.1, 6.2, 13, 16 and 17.
7.2 Ongoing clinical trials
Purpose and disclosure boundary
Discuss important emerging findings without compromising trial integrity or presenting unstable unblinded data as final. State data maturity and whether treatment assignment is known.
Biological-specific reasoning
Emerging cytokine-release, hypersensitivity, infection, laboratory or immunogenicity patterns may require urgent action before trial completion. Product version and batch must remain traceable within trial supply.
mAb-X example
An ongoing Disease B trial has three delayed reactions under blinded treatment. The report states the blinded aggregate and monitoring action; it does not attribute all three to mAb-X.
Common error
Do not omit important action because a study remains ongoing, and do not overinterpret pooled blinded data.
7.3 Long-term follow-up
Purpose and inputs
Summarise delayed, persistent or cumulative outcomes after protocol treatment. Long-term follow-up may be particularly important for durable immune effects, malignancy, chronic infection, persistent antibodies or delayed pregnancy outcomes.
mAb-X reasoning
Classify follow-up from last dose and cumulative exposure. Explain attrition: participants remaining in follow-up may differ from those lost. Persistent anti-drug antibodies without clinical consequence are not automatically an adverse outcome.
7.4 Other therapeutic use
Scope
Include significant findings from expanded access, named-patient, compassionate-use or other organised therapeutic programmes not already reported. Describe the data-collection system because it affects source classification and completeness.
Biological-specific reasoning and example
Severely ill populations may have different baseline risk and concomitant immunosuppression. In an mAb-X access programme, infection counts require comparison with clinical context rather than direct contrast with a trial population.
7.5 New safety data related to fixed combinations
Applicability
Use this subsection when the product is a fixed combination. If not applicable, state so rather than inventing content. Combination administration outside a fixed-combination product belongs in the appropriate trial or interaction discussion.
Biological-specific reasoning
For a biological combination, distinguish component risks, pharmacodynamic interaction, administration sequence and device or co-pack contribution.
Reconciliation
All Section 7 conclusions should flow to Sections 15–18 where material. The output is a controlled account of trial evidence that changes or tests the safety model.
Section 8: Findings from Non-Interventional Studies
Regulatory purpose
Section 8 evaluates important findings from studies in which treatment is not assigned by the study protocol. These studies may characterise actual use, comparative safety, long latency and uncommon populations.
Evidence inputs
Include registries, database studies, post-authorisation safety studies, chart reviews and other relevant observational designs. State design, population, index date, exposure definition, comparator, outcome definition, confounder control, follow-up, missingness and result precision.
Biological-specific reasoning
Product identification is central. A database containing only the active substance cannot validly compare reference and biosimilar brands. Switching studies require time-varying exposure, switch reason, number and direction of switches, disease activity and nocebo-related discontinuation considerations without assuming causation.
Immunogenicity studies must link assay platform, sample timing, drug concentration, antibody persistence and clinical outcome. Different assays cannot be pooled merely because each reports “ADA positive.”
mAb-X example
A cohort reports higher antibody positivity after switching to a biosimilar. The PBRER examines baseline antibodies, intensified post-switch sampling, assay change, drug trough levels and loss-of-response outcomes. If sampling was more frequent after switching, detection bias may explain part of the difference.
Common errors, reconciliation and output
Do not describe adjusted association as proof or ignore exposure misclassification. Reconcile with Sections 5, 15–18. The output is a qualified estimate or pattern with explicit residual uncertainty.
Section 9: Information from Other Clinical Trials and Sources
Purpose and scope
Capture important clinical evidence not already placed in Sections 7 or 8: pooled analyses, meta-analyses, investigator-sponsored trials, partner data, pharmacology studies and relevant data from related products.
Biological-specific reasoning
Class or target evidence may support plausibility, but molecular architecture, effector function, tissue penetration, conjugated payload, dose and population can change risk. Explain why evidence is transportable—or why it is not.
mAb-X example
A meta-analysis of target-T inhibitors suggests opportunistic infection risk. mAb-X trials show stable rates. The section explains target plausibility while reserving product-specific characterisation for Section 16.4.
Common errors and reconciliation
Prevent double counting when pooled analyses include trials already summarised. Reconcile with Sections 7, 11, 15 and 16. The output is contextual clinical evidence, not a second signal evaluation.
Section 10: Non-Clinical Data
Regulatory purpose
Section 10 presents new non-clinical findings with potential clinical safety relevance. It is not a catalogue of routine quality testing.
Evidence inputs
Consider pharmacology, toxicology, tissue cross-reactivity, cytokine-release assays, reproductive or juvenile studies, impurity and aggregate investigations, extractables and leachables, container-closure studies and comparability assessments. State model, test system, exposure, endpoint and translational limitation.
Biological-specific reasoning
Biological activity may be species-specific, making conventional animal models poorly informative. Explain model relevance rather than equating absence of animal toxicity with human safety. For manufacturing changes, distinguish an analytical difference from a clinically meaningful difference. Comparability is the evidence-based demonstration that pre-change and post-change product remain highly similar in relevant quality attributes and that observed differences do not adversely affect safety or efficacy.
mAb-X example
The site transfer produces a small glycan-distribution shift within an approved range and unchanged Fc-mediated functional assays. The correct conclusion is that no new clinical safety implication is identified from current comparability evidence, with continued surveillance. “The products are identical” and “the shift created immunogenicity” would both exceed the evidence.
Common errors, reconciliation and output
Do not reproduce confidential quality detail without explaining clinical relevance. Reconcile material findings with Sections 3, 15, 16 and 19. The output is a translational conclusion and, where needed, a monitoring action.
Section 11: Literature
Regulatory purpose
Section 11 identifies and evaluates published safety, efficacy and benefit–risk evidence relevant during the interval.
Search inputs and reproducibility
Record databases, search dates, interval, product names, active substance, previous names, brands, biosimilar identifiers, target/class terms, adverse-event concepts, immunogenicity, formulation, device and quality terms. Maintain search strategy and screening records.
Evidence hierarchy and reasoning
A published case may contribute detailed chronology but cannot estimate frequency. A mechanistic study may support plausibility but not clinical causality. A comparative observational study may estimate association but remain vulnerable to confounding. A systematic review may synthesise evidence but inherit limitations of included studies.
mAb-X example
A case series describes delayed hypersensitivity after different mAb-X batches. The diversity of batches weakens a single-batch hypothesis, while compatible timing and phenotype strengthen the product-level signal. Denominator absence prevents frequency estimation.
Common errors, reconciliation and output
Do not provide an annotated bibliography or cite only review articles for decisive claims. Explain duplicate overlap with company cases. Reconcile with Sections 6, 9, 15–18.
Section 12: Other Periodic Reports
Regulatory purpose
Section 12 reconciles relevant periodic reports prepared for another region, partner, co-development arrangement, combination product or related reporting scope.
Inputs and scope comparison
For each report record holder, product, territory, interval, DLP, RSI, indications, presentations and conclusion. Apparent disagreement may result from different evidence boundaries rather than different medical judgement.
Biological-specific reasoning
Partners may market different formulations, devices or manufacturing versions. A partner report including SC exposure cannot be treated as directly equivalent to a report covering only IV use.
mAb-X example
A partner report identifies more administration reactions because it includes the SC injector and a broader event definition. After harmonising route and definition, the systemic reaction pattern is consistent.
Common errors, reconciliation and output
Do not paste another report's conclusion. Explain compatibility, difference and implication. Reconcile with Sections 2, 5, 15 and 16.
Section 13: Lack of Efficacy in Controlled Clinical Trials
Regulatory purpose
Section 13 evaluates clinically important lack of efficacy in controlled trials, especially where therapeutic failure may produce serious outcomes.
Define the phenomenon
Distinguish:
- primary non-response;
- secondary loss of response;
- delayed response;
- disease progression;
- inadequate exposure;
- device underdelivery;
- neutralising antibodies;
- endpoint or adherence artefact.
These are not interchangeable causal explanations.
Evidence inputs and analysis
Use prespecified efficacy endpoints, rescue therapy, discontinuation, pharmacokinetics, pharmacodynamics, drug concentration, anti-drug antibodies, administration records and device data. Compare groups using the trial estimand and time window; individual reports should not replace the controlled analysis.
mAb-X example
A participant loses response after an incomplete SC injection. This case supports a delivery-failure pathway, not failure of the antibody mechanism. Separate it from participants with adequate exposure and persistent disease.
Common errors, reconciliation and output
Do not count MedDRA “drug ineffective” terms as an efficacy analysis. Reconcile with Sections 7, 15–18 and quality/device investigations.
Section 14: Late-Breaking Information
Regulatory purpose
Section 14 addresses important information received after the DLP but before report finalisation. It preserves both scientific responsibility and reproducibility.
Inclusion test
Include information when it could materially change a signal, risk characterisation, benefit–risk conclusion, action or assessor understanding. State receipt date, source, preliminary status and effect on conclusions.
Biological-specific reasoning
Examples include a confirmed batch defect, post-DLP recall, major immunogenicity result, new device cluster, important study result or regulatory action. Do not silently add these cases to locked interval tables.
mAb-X example
Two serious delayed-hypersensitivity cases arrive after the DLP. They appear in Section 14, update the cumulative medical interpretation and may influence Section 19, while Section 6 interval counts remain unchanged.
Common errors, reconciliation and output
Avoid both extremes: ignoring material evidence and reopening every interval table. Reconcile with the executive summary and Sections 15–19.
Section 15: Overview of Signals
A safety signal is information suggesting a new potentially causal association, or a new aspect of a known association, that warrants further investigation. It is a hypothesis requiring management, not proof of a risk.
Regulatory purpose
Section 15 provides the controlled signal inventory at the DLP. It enables the assessor to see which hypotheses were new, ongoing or closed and where their full evaluations appear.
Required signal table fields
For each signal include:
- standardised signal name;
- date first detected;
- date entered the signal process;
- evidence source;
- status at interval start and DLP;
- date closed where applicable;
- reason for status;
- product or population scope;
- location of evaluation.
Use governance dates consistently. A signal completed after the DLP remains ongoing at the DLP and may be updated in Section 14.
Biological attribution field
Add an explicit hypothesis level:
| Level | Question |
|---|---|
| Target/class | Could pharmacology shared across products explain the event? |
| Active substance | Does evidence extend across products containing the substance? |
| Product | Is one authorised product implicated? |
| Batch/manufacturing period | Is evidence temporally and distributively clustered? |
| Formulation/route | Does exposure pathway explain the pattern? |
| Device | Is delivery-system performance implicated? |
| Use process | Do storage, preparation or administration explain the event? |
This field does not predetermine the conclusion. It ensures that the signal question is testable.
Evidence-state reasoning
“New,” “ongoing” and “closed” describe process state. A closed signal may result in an identified risk, continued monitoring, insufficient evidence or refutation. Use a concise rationale rather than an unexplained status label.
mAb-X signal table
| Signal | DLP status | Main evidence | Initial scope | Evaluation location |
|---|---|---|---|---|
| Delayed hypersensitivity | Ongoing | Spontaneous cases, literature, mechanism | Product/route unresolved | 16.2 and 14 |
| Incomplete injector dose | Closed as device problem | Complaints, returned-device testing | SC device lot L17 | 16.2 and 16.5 |
| Increased serious infection | Closed without new product finding | Trials, registry, class evidence | Target/class | 16.2 and 16.4 |
| Switch-associated immunogenicity | Under monitoring; not validated as signal | Observational cohort | Product sequence | 8 and 16.3 |
The last row illustrates discipline: interesting evidence does not automatically become a validated signal.
Common errors
- listing adverse events rather than controlled signals;
- calling a signal closed without its conclusion;
- changing status dates between tables;
- assigning all biological signals to the active substance;
- omitting signals completed during the interval;
- duplicating the full evaluation instead of cross-referencing it.
Cross-section reconciliation and output
New or closed signals must reconcile with Sections 3, 4, 14, 16 and 19. Section 15 outputs the inventory; Section 16 outputs the medical evaluation.
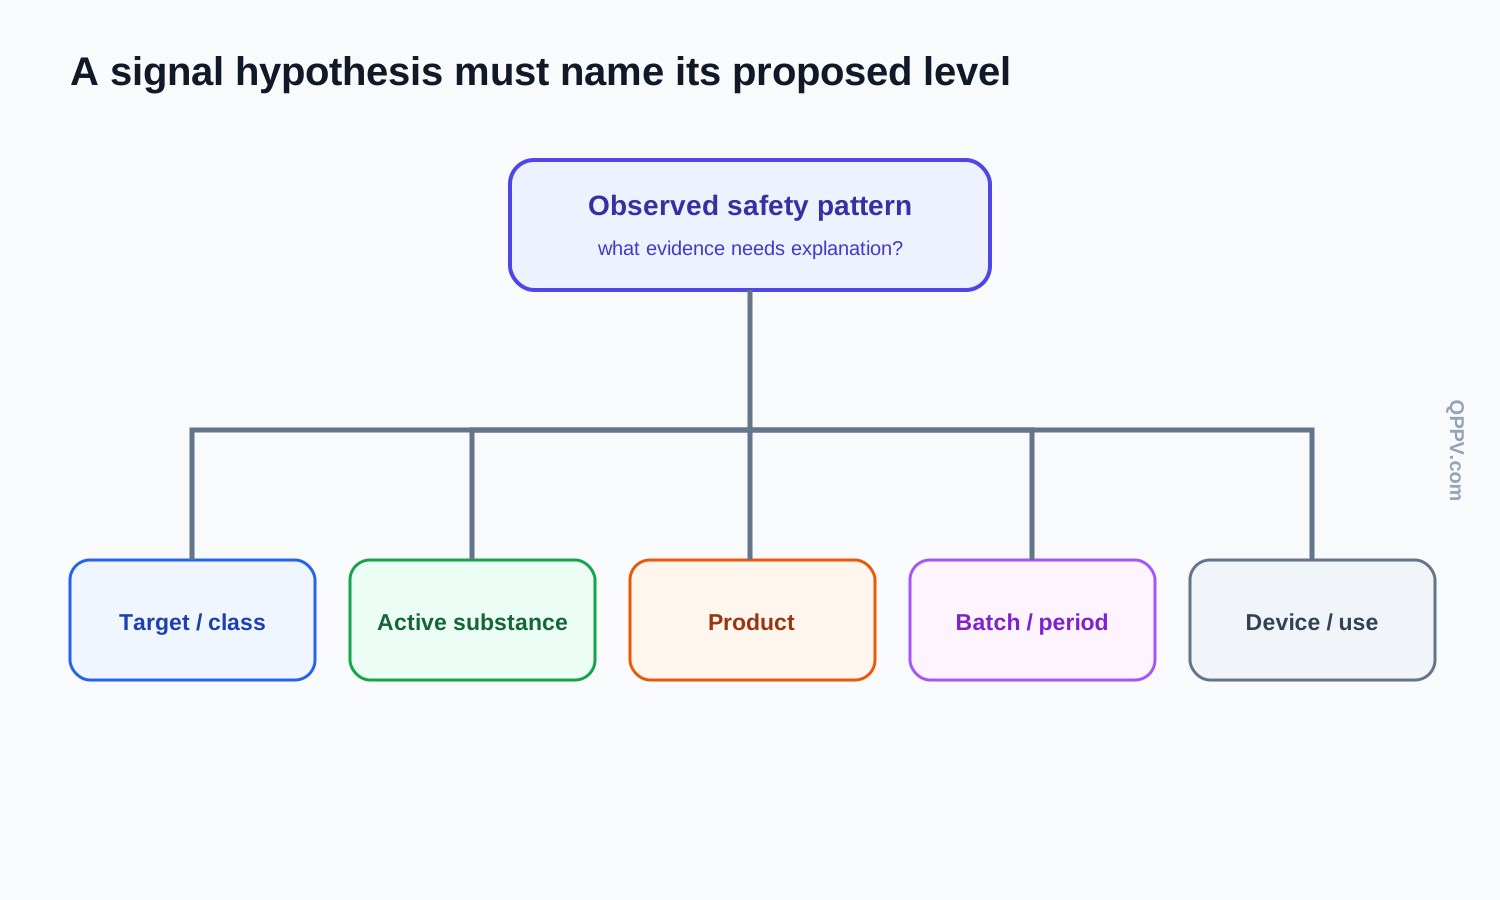
Figure 3. Biological signal hypotheses may concern target/class, active substance, product, batch, formulation, device or use process. The PBRER should test rather than assume the correct level.
Section 16: Signal and Risk Evaluation
Section 16 is the principal safety reasoning component. It has four distinct functions: establish the safety-concern baseline, present completed signal evaluations, analyse new information about known risks and then reconstruct cumulative risk characterisation. Risk-minimisation effectiveness is assessed where applicable.
16.1 Summary of safety concerns
Regulatory purpose
Section 16.1 states the important identified risks, important potential risks and important missing information applicable at the beginning of the interval. It establishes the baseline against which interval changes are interpreted.
An identified risk has adequate evidence of association. A potential risk has a suspected association for which evidence is insufficient to conclude causality. Missing information concerns gaps in knowledge about use in populations or circumstances that could be clinically significant. “Important” reflects potential effect on benefit–risk or implications for public health, risk minimisation or further evaluation.
Inputs
Use the applicable RMP, prior PSUR, regulatory decisions and safety governance records. If there is no RMP, justify the proposed list using scientific and clinical evidence.
EU reconciliation nuance
The PSUR and RMP serve related but different purposes. Current EU explanatory material recognises that their lists may differ; do not mechanically force identity or apply RMP removal logic to the PSUR without analysis. State the source and explain differences, additions, reclassifications or removals.
Biological-specific structure
Where useful, organise concerns by:
- active-substance or target risk;
- route/formulation/device risk;
- product or batch risk;
- population-specific risk;
- important uncertainty concerning immunogenicity, switching or long-term exposure.
mAb-X example
Serious infection is an important identified target-related risk. Delayed hypersensitivity remains an ongoing signal at interval start and is not yet an identified risk. Limited long-term Disease B exposure is missing information. L17 injector underdelivery is a device issue requiring control, but its classification in the safety-concern framework depends on clinical importance and the applicable RMP.
Common errors and output
Do not copy a list without effective dates or rationale. The output is the safety baseline used by Sections 16.3, 16.4, 18 and 19.
16.2 Signal evaluation
Regulatory purpose
Section 16.2 presents evaluations of signals completed during the interval. It should answer the predefined signal question using cumulative evidence, state the conclusion and explain action.
Define the signal question
A useful question specifies exposure, event, population and attribution level:
Does mAb-X increase delayed systemic hypersensitivity occurring more than six hours after administration, and does the pattern differ by IV versus SC presentation?
“Review hypersensitivity” is too broad to determine relevant cases or evidence.
Evidence assembly
For each signal integrate:
- case definition and search strategy;
- case series with chronology, dechallenge, rechallenge and alternatives;
- reporting pattern and exposure context;
- trial and observational evidence;
- literature and class/target evidence;
- pharmacology and immunology;
- product quality, batch, device and manufacturing evidence;
- relevant regulatory or partner information.
A negative source should be weighted by its capacity to detect the outcome. A small trial cannot strongly refute a rare delayed reaction.
Biological-specific stratification
Begin broad enough to detect a shared effect, then stratify by product identity, batch, route, formulation, device, manufacturing period, switching sequence and anti-drug-antibody status where data support it. Report missing product identity because it can distort apparent product differences.
Causal reasoning
Separate:
- temporal compatibility;
- phenotype consistency;
- biological plausibility;
- dechallenge and rechallenge;
- alternative causes;
- dose or exposure response;
- internal consistency across sources;
- specificity of product attribution.
Absence of a batch cluster weakens a batch hypothesis; it does not refute product-wide immunogenicity.
mAb-X example: delayed hypersensitivity
The case series shows compatible delayed timing, several serious cases and no single-batch concentration. Both routes are represented, but route is unknown in many cases. Class literature supports immune plausibility; trial power for rare events is limited. The conclusion may be that a causal association is reasonably supported at product level, with insufficient evidence of route or batch specificity. Proposed action: RSI and regional product-information evaluation plus targeted follow-up.
mAb-X example: incomplete injector dose
Returned-device testing confirms a component malfunction concentrated in L17. Clinical consequences are reduced exposure and disease deterioration in a subset. This supports device/lot attribution rather than active-substance inefficacy. The signal closes into quality/device corrective action and effectiveness monitoring.
Common errors, reconciliation and output
Do not present case counts without a case definition, ignore contradictory evidence or close a signal with “no new concern” alone. Reconcile conclusions with Sections 4, 15, 16.4, 16.5 and 19.
16.3 Evaluation of risks and new information
Regulatory purpose
Section 16.3 evaluates interval evidence relevant to previously recognised risks and missing information. It asks whether cumulative understanding changed even when no new signal evaluation was completed.
Risk-by-risk analytical frame
For each risk with material new evidence state:
- previous characterisation;
- new interval evidence;
- evidentiary limitations;
- cumulative interpretation;
- change in frequency, severity, outcome, risk group, preventability or mechanism;
- effect on safety concern, pharmacovigilance or risk minimisation.
It is not necessary to reproduce all confirming data. Detail should be proportionate to importance and change.
Important potential risks
Actively assess whether new evidence moves a potential risk toward confirmation, refutation or continued uncertainty. “No new cases” is weak evidence if exposure is low or outcome recognition is poor.
Missing information
Evaluate new data from previously understudied populations or circumstances. Increased exposure does not automatically close missing information; the evidence must be sufficient to characterise relevant benefits and risks.
Biological-specific reasoning
Examine whether a new formulation, device, manufacturing change or biosimilar-switching pattern changes exposure to a known risk. Consider immunogenicity assay comparability and product traceability before interpreting product differences.
mAb-X example: serious infection
Trial and registry rates remain stable, with no new severity pattern. Disease B exposure remains limited. The identified infection risk remains unchanged, but confidence in the new indication is lower because follow-up is shorter.
mAb-X example: switching and antibodies
The cohort supplies new information but sampling intensity and assay changes limit inference. Switching-associated immunogenicity remains unconfirmed; targeted data collection continues.
Common errors, reconciliation and output
Do not duplicate Section 16.2 or discuss only evidence that reached a signal threshold. Reconcile with Sections 8, 15, 16.4, 17–19.
16.4 Characterisation of risks
Section 16.4 reconstructs important identified and potential risks from cumulative evidence and describes important missing information. It is not a copy of Section 16.3. Section 16.3 asks, “What did interval evidence change?” Section 16.4 asks, “What is the best current cumulative model of this risk?”
A useful risk-characterisation entry behaves like a scientific profile: it defines the outcome and scope, quantifies what can validly be quantified, describes clinical consequences and risk modifiers, explains mechanism and uncertainty, and connects the result to prevention and benefit–risk.
16.4.1 Define the risk and attribution level
Begin with a medically precise definition. Specify included diagnoses, severity spectrum, time window and exclusions. Then state whether current evidence supports target/class, active-substance, product, formulation/route, batch, device or use-process attribution.
mAb-X example: “Serious opportunistic infection associated with target-T inhibition” is a target-related risk. “Incomplete dose due to L17 injector component failure” is a device/lot issue. Combining them under “treatment complications” destroys analytical specificity.
Reasoning: the definition controls the numerator, evidence search, denominator and preventability analysis. If it changes between sections, estimates cannot reconcile.
16.4.2 Frequency, numerator and denominator
Frequency requires a compatible numerator and denominator.
- The numerator is the number of persons or events meeting the defined outcome.
- The denominator is the population and time in which those outcomes could be ascertained.
- Precision expresses statistical uncertainty, commonly through a confidence interval.
State whether the estimate is incidence proportion, incidence rate, prevalence or reporting proportion. Spontaneous reports ordinarily lack systematic outcome ascertainment and a reliable common denominator; a reporting rate based on distributed doses is not clinical incidence.
For trial or registry estimates provide number of affected participants, number exposed or person-time, observation window, censoring and confidence interval. If data are too sparse, state a range or qualitative frequency with justification rather than false precision.
mAb-X example: serious-infection incidence is estimated from trials and a registry with defined follow-up. Delayed-hypersensitivity spontaneous reports are described by case count and reporting pattern, not assigned an incidence from sales.
Biological reasoning: choose product-wide exposure for a product-level risk, route-specific exposure for an administration risk and affected-device units for a device failure. Unknown product identity belongs in uncertainty, not an invented stratum.
16.4.3 Absolute and relative risk
Absolute risk describes event probability or rate in the exposed population. Relative risk compares that risk with an appropriate comparator. Both require precision and context.
A relative risk of 2 can represent an increase from 1 to 2 per 100,000 or from 10 to 20 per 100; clinical implications differ. Comparator selection must address disease severity, concomitant therapy and calendar time.
mAb-X example: a registry hazard ratio for infection is interpreted with its confidence interval, absolute rate difference and residual confounding. If Disease A patients receiving mAb-X are more immunosuppressed than comparator patients, adjusted analysis reduces but may not eliminate channeling bias.
16.4.4 Seriousness, severity and patient impact
Seriousness is a regulatory classification based on outcome or required intervention. Severity is clinical intensity. Describe fatality, hospitalisation, disability, treatment, intensive care, symptom burden, quality of life and effect on treatment continuity.
Separate immediate reaction burden from downstream consequences. A non-serious injector failure can lead to clinically important disease flare; a severe injection-site reaction may remain non-serious.
mAb-X example: delayed hypersensitivity ranges from self-limited rash to bronchospasm requiring hospitalisation. Report distribution and uncertainty rather than letting the most dramatic case represent all cases.
16.4.5 Public-health impact
Public-health impact combines individual consequence with number exposed, preventability, detectability, affected population and potential system burden. A rare fatal event in a widely used product may be important; a frequent mild reaction may substantially affect adherence.
For a biological, consider specialist administration, cold-chain systems, screening capacity, vaccination, infusion resources and device replacement. Avoid unsupported multiplication of an uncertain spontaneous frequency by total sales.
mAb-X example: the L17 issue has limited lot distribution and is rapidly correctable, containing public-health impact. Opportunistic infection applies across a larger cumulative population and requires sustained controls.
16.4.6 Patient and disease risk factors
Evaluate age, pregnancy, lactation, renal or hepatic impairment, comorbidity, immune status, disease severity, prior infection, genetics, concomitant immunosuppression and previous biological exposure.
A risk factor changes the probability or consequence of the outcome; it is not merely common among cases. Compare with an appropriate exposed reference population and acknowledge confounding.
mAb-X example: corticosteroid use and baseline lymphopenia are more frequent among serious-infection cases, but Disease A severity influences both treatment choice and infection risk. The report describes adjusted evidence and residual uncertainty.
16.4.7 Dose, route, duration and risk window
Characterise dose relationship, loading versus maintenance, route, formulation, treatment duration, cumulative exposure, time since first dose and time since last dose. Define the risk window—the period in which exposure could plausibly contribute.
Biological half-life and pharmacodynamic persistence may extend risk after discontinuation. Route may affect local reactions, systemic peak exposure or administration processes without changing target biology.
mAb-X example: infection risk is evaluated during treatment and a justified post-dose period. Hypersensitivity timing is separated into immediate and delayed phenotypes. Injector failures concern individual administration episodes, not cumulative molecular exposure.
16.4.8 Preventability and detectability
Describe whether risk can be prevented, predicted, detected early or mitigated. Consider screening, contraindications, vaccination, laboratory monitoring, premedication, infusion observation, patient education, traceability, device training and batch action.
A process measure is not proof of prevention. Distribution of a guide shows reach; correct screening or reduced avoidable events is closer to effectiveness.
mAb-X example: infection risk is partly preventable through screening and clinical monitoring, but not eliminated. L17 underdelivery is preventable through removal and replacement of affected devices.
16.4.9 Reversibility and clinical course
Characterise time to recovery, persistence, recurrence, sequelae, treatment response, dechallenge and rechallenge. Long half-life may delay improvement after stopping therapy. Rechallenge may be medically inappropriate after serious reactions.
mAb-X example: most delayed-hypersensitivity cases resolve with treatment, but recurrence information is sparse because re-exposure is often avoided. State this as informative missing evidence, not as absence of recurrence.
16.4.10 Mechanism and biological plausibility
Explain established or hypothesised mechanisms: target pharmacology, immune complex formation, anti-drug antibodies, cytokine release, excipient response, aggregate-related immunogenicity, contamination, altered delivery or disease interaction.
Mechanism should fit phenotype, timing and exposure. A plausible mechanism increases coherence but does not prove causality. Multiple mechanisms may produce similar clinical terms.
mAb-X example: delayed hypersensitivity could involve immune mechanisms, but available ADA results are incomplete and assays were collected at inconsistent times. The mechanism remains plausible but unresolved.
16.4.11 Evidence strength, uncertainty and conflict
Describe evidence source quality, consistency, dose or temporal gradient, specificity, bias, missingness and precision. Present conflicting evidence explicitly.
Use a structured hierarchy rather than a simplistic score:
| Evidence | Contribution | Principal limitation |
|---|---|---|
| Well-documented cases | Phenotype and timing | Reporting selection; no denominator |
| Randomised trials | Controlled comparison | Limited power for rare events |
| Registry | Larger actual-use population | Confounding and exposure misclassification |
| Mechanistic data | Plausibility | Indirect clinical inference |
| Quality investigation | Product/batch specificity | May not explain all clinical cases |
mAb-X example: case and mechanistic evidence support delayed hypersensitivity, trials neither confirm nor strongly refute it, and no batch pattern appears. The conclusion states both association confidence and attribution uncertainty.
16.4.12 Missing information
Describe limitations in studied numbers, duration, populations, products, formulations, switching sequences and long-term use. Missing information is not a list of every absent datum; focus on gaps that may alter benefit–risk or risk control.
For biologicals, relevant gaps may include pregnancy, paediatrics, severe immunosuppression, repeated switching, long-term immunogenicity, home administration, new devices or post-manufacturing-change experience.
mAb-X example: Disease B has short follow-up and limited exposure in older immunosuppressed patients. Repeated-switch immunogenicity data are incomplete. State how ongoing studies or routine surveillance address the gaps.
Building the final risk-characterisation table
| Dimension | Serious infection | Delayed hypersensitivity | L17 underdelivery |
|---|---|---|---|
| Attribution | Target/product | Product; route unresolved | Device/lot |
| Frequency evidence | Trial/registry incidence | Spontaneous pattern; incidence unknown | Complaints per distributed affected units |
| Patient impact | Potentially fatal | Mild to serious | Disease deterioration possible |
| Main risk factors | Immunosuppression, disease severity | Uncertain | Affected device |
| Preventability | Screening/monitoring partly effective | Recognition and management | Lot removal/replacement |
| Key uncertainty | New-indication exposure | Mechanism and route | Residual devices in use |
The table summarises the reasoning; it cannot replace the supporting analysis.
16.5 Effectiveness of risk minimisation
Regulatory purpose
Section 16.5 evaluates whether measures intended to prevent or reduce a risk are achieving their objectives. In the EU, detailed results of effectiveness evaluation may be presented in the regional appendix as specified by current guidance; the main report should integrate the implication for the risk and benefit–risk balance.
Define the intervention and objective
For each measure specify:
- risk addressed;
- target population and setting;
- routine or additional measure;
- intended behavioural or clinical change;
- implementation date and coverage;
- process and outcome indicators;
- prespecified success criteria where applicable.
Without a defined objective, activity cannot be interpreted as effectiveness.
Process, knowledge, behaviour and clinical outcomes
Use a progression:
- implementation — material distributed, systems activated, training offered;
- reach — intended professionals or patients received the measure;
- knowledge — critical information was understood;
- behaviour — screening, prescribing or administration changed;
- clinical outcome — preventable risk or severity decreased.
Later levels provide stronger evidence of risk reduction but may be harder to attribute exclusively to the measure.
Biological-specific measures
Relevant controls may include infection screening, vaccination, infusion monitoring, laboratory surveillance, pregnancy prevention, traceability, cold-chain instructions, reconstitution training, device-use education and batch/device recall.
Assess the correct denominator. Device training effectiveness is evaluated among users of that device, not all active-substance exposure. Batch recall effectiveness is evaluated against affected units distributed, recovered, replaced or confirmed unused.
mAb-X example
For L17, measure implementation is the field correction; reach is confirmation that affected sites and patients were contacted; behaviour is replacement before use; outcome is absence of further incomplete-dose events from units remaining in circulation. The number of letters sent alone cannot demonstrate effectiveness.
For serious infection, screening completion and correct management of positive results are more informative than availability of educational material. Clinical infection rates require adjustment for changes in population and concomitant immunosuppression.
Bias, limitations and reasoning
Before–after changes can reflect publicity, stimulated reporting, secular trends or changing exposure. A temporary rise in reports after communication may show increased awareness rather than increased true incidence. State design limitations and triangulate several indicators.
Common errors, reconciliation and output
Do not equate distribution with effectiveness, use an unrelated denominator or ignore country-level implementation differences. Reconcile with Sections 3, 16.4, 18, 19 and the EU regional appendix. The output is a decision to maintain, modify, strengthen or retire the measure, with rationale.
Section 17: Benefit Evaluation
Benefit evaluation ensures the PBRER does not treat safety in isolation. Efficacy commonly refers to effects under controlled study conditions; effectiveness refers to effects in actual clinical use. The distinction is not absolute in every design, but it helps organise evidence.
17.1 Important baseline efficacy and effectiveness information
Purpose
Summarise the established benefits that form the reference point for interval evaluation. Focus on outcomes that matter to the benefit–risk decision, not the complete clinical overview.
Evidence inputs
Use pivotal and supportive trials, established long-term evidence, validated patient-reported outcomes, survival, disease control, functional outcomes and important subgroup evidence. State indication, population, comparator, outcome definition, effect size and durability.
Biological-specific reasoning
Mechanism and product architecture may support extrapolation across indications for biosimilars, but the PBRER should not re-litigate authorisation. It should accurately state the benefit evidence applicable to the holder's product and indications. Route or device may change convenience, adherence or delivery without changing molecular efficacy.
mAb-X example
Disease A has substantial reduction in severe flares and established long-term benefit. Disease B has a moderate symptom and function benefit over a shorter evidence period. These are separate baselines for Section 18.
Common errors and output
Do not describe benefits with adjectives alone. Avoid mixing relative and absolute effects without baseline risk. The output is a concise benefit reference model.
17.2 Newly identified information on efficacy and effectiveness
Purpose and inputs
Evaluate interval findings that could change benefit magnitude, durability, affected population or confidence. Include new trials, extensions, observational effectiveness, resistance, treatment persistence, adherence and comparative data.
Biological-specific reasoning
Assess whether device underdelivery, cold-chain failure, switching or immunogenicity changes actual exposure or effectiveness. Separate pharmacological loss of effect from administration failure and nocebo-related discontinuation.
mAb-X example
Disease B extension data support maintained benefit to one year, while the L17 device problem causes isolated underexposure. The latter affects delivery reliability rather than the antibody's intrinsic efficacy.
Common errors and reconciliation
Do not use spontaneous “drug ineffective” counts as an effectiveness estimate. Reconcile with Sections 7, 8, 13 and 16.
17.3 Characterisation of benefits
Dimensions
Characterise:
- magnitude and clinical importance;
- durability and time to benefit;
- proportion responding;
- consequences of non-response;
- affected subgroups;
- impact on survival, function, symptoms or quality of life;
- convenience or treatment burden where clinically meaningful;
- certainty and limitations.
mAb-X example
Disease A benefit is large in a severe population with few alternatives. Disease B benefit is moderate in a less severe population with several options. The same rare serious risk therefore carries different relative weight.
Common errors, reconciliation and output
Do not collapse indications into an average benefit. Reconcile with Section 5 exposure, Section 18 context and Section 19 actions.
Section 18: Integrated Benefit–Risk Analysis
Integration means judging benefits and risks in the same indication, population, product configuration and clinical context. It is not the juxtaposition of a safety summary and an efficacy summary.
18.1 Benefit–risk context: medical need and alternatives
Regulatory purpose
Define disease seriousness, natural history, untreated outcome, treatment goals, current alternatives, population and place in therapy. Context determines how benefits, risks and uncertainties are valued.
Biological-specific reasoning
Consider availability of other target mechanisms, reference products, biosimilars, alternative routes and non-biological treatments. Do not assume a biosimilar has a different benefit–risk balance solely because it is a different product; use evidence.
mAb-X example
Disease A is severe and refractory with few alternatives. Disease B is moderate with several effective treatments. Infection risk may be acceptable under controls in both, but uncertainty about delayed hypersensitivity or device reliability may influence choices differently.
Common errors and output
Avoid generic disease burden copied from an introduction. The output is the decision context for Section 18.2.
18.2 Benefit–risk analysis evaluation
Assemble decision-driving effects
Identify rather than list:
- principal established benefits;
- important identified risks;
- important potential risks;
- material uncertainty;
- effectiveness of controls;
- subgroup or presentation differences;
- interval changes.
State which factors actually drive the conclusion.
Align populations and time horizons
Compare benefits and risks in the same indication and population. Account for onset and duration: rapid benefit may coexist with cumulative infection risk; durable pharmacodynamic effects can persist after discontinuation.
Compare unlike outcomes transparently
Benefits and risks may use different measures. Do not force a numerical score unless a valid method, assumptions and sensitivity analysis are provided. A structured qualitative framework can be rigorous when evidence and value judgements are explicit.
| Dimension | Disease A | Disease B | Interpretation |
|---|---|---|---|
| Benefit magnitude | Large | Moderate | Different clinical need |
| Serious infection | Established, controlled | Less mature evidence | Target-related risk |
| Delayed hypersensitivity | Emerging product risk | Emerging product risk | Frequency uncertain |
| L17 underdelivery | SC users only | SC users only | Correctable device/lot issue |
| Long-term uncertainty | Moderate | Higher | Shorter Disease B follow-up |
Evaluate uncertainty
State whether uncertainty could plausibly reverse the conclusion. Identify what information would be decision-changing and how it will be obtained. “More data are needed” is insufficient without specifying the question.
mAb-X conclusion reasoning
The benefit–risk balance remains favourable for both indications under authorised conditions. Confidence is higher in Disease A. Delayed hypersensitivity supports product-information evaluation and enhanced case follow-up. L17 does not imply molecular inefficacy; field-action effectiveness is monitored. Disease B long-term infection and benefit durability remain important uncertainty.
Common errors and reconciliation
Do not claim favourable balance solely because exposure increased without regulatory action. Reconcile every driver with Sections 5, 16, 17 and 19.
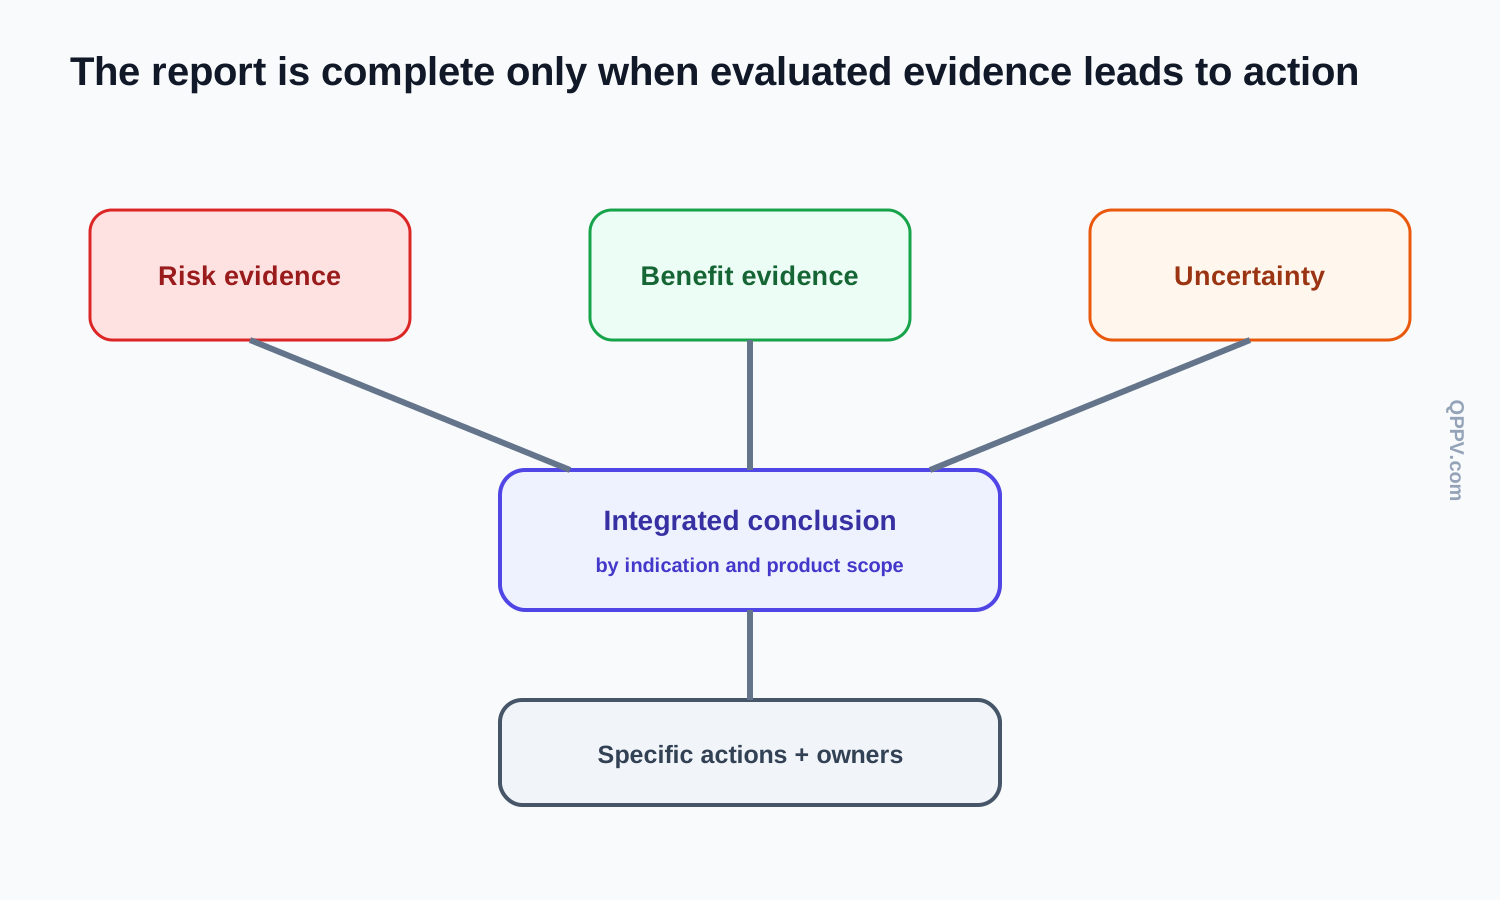
Figure 4. The integrated conclusion combines benefit, risk, uncertainty, product scope and effectiveness of controls. Different indications or presentations may require separate judgements.
Section 19: Conclusions and Actions
Regulatory purpose
Section 19 states whether the safety profile or benefit–risk balance changed and specifies proposed or completed actions. It is the decision output of the report.
Required conclusion structure
For each indication or materially different presentation state:
- benefit–risk conclusion;
- change from prior conclusion;
- important new safety or benefit finding;
- remaining uncertainty;
- action, rationale and regulatory pathway.
Distinguish action already completed, action proposed to authorities and internal follow-up.
Biological-specific actions
Possible actions include RSI or regional product-information change, RMP update, targeted follow-up, post-authorisation study, enhanced batch traceability, manufacturing surveillance, device corrective action, training, batch recall or additional risk minimisation.
mAb-X example
- Benefit–risk remains favourable for Disease A and Disease B.
- Delayed hypersensitivity is supported as a product-level risk; wording and risk-management changes are proposed.
- Evidence does not support batch or route specificity.
- L17 underdelivery remains a device/lot issue; field-action effectiveness continues.
- The site transfer does not change the benefit–risk conclusion on current evidence.
- Disease B long-term follow-up remains necessary.
Common errors, reconciliation and output
Avoid “continue routine monitoring” without connecting it to a conclusion. Reconcile with the executive summary, Sections 3, 4, 15–18 and the proposed regulatory submission.
Section 20: Appendices
Regulatory purpose
Appendices supply required supporting material without interrupting the main reasoning. They are part of the report and must be internally consistent.
Typical content
Include applicable RSI, signal tabulations, study listings and regional appendices. The EU regional appendix contains EU-specific information required by GVP Module VII and current procedural guidance.
Biological-specific supporting tables
Where decision-useful, include:
- exact-brand and batch completeness;
- route/formulation exposure;
- switching sequence definitions;
- immunogenicity assay characteristics;
- manufacturing-period or device-lot analysis;
- complaint-to-ICSR reconciliation.
Do not relocate essential reasoning to an appendix.
mAb-X example
An appendix describes ADA assays and sampling schedules so the main text can explain why positivity estimates cannot be pooled. Another table reconciles L17 complaints, returned devices and ICSRs with clinical consequences.
Common errors, reconciliation and output
A signal cannot be ongoing in an appendix and closed in Section 15 without a dated explanation. Verify product names, DLP, totals, study status, RSI version and action status against the body.
Authoring workflow and governance
A granular article does not imply that the PBRER should be written as disconnected templates. The authoring system must preserve one chain of reasoning across functions and sections.
Section-to-source planning matrix
Before drafting, define every data package:
| PBRER area | Principal source/owner | Cut and scope | Biological-specific control |
|---|---|---|---|
| Approval status | Regulatory affairs | DLP/current status | Brand, route, device, indication |
| RSI changes | Labelling/safety governance | Interval version history | Product versus presentation wording |
| Exposure | Clinical, commercial, epidemiology | Interval/cumulative | Denominator assumptions and strata |
| Cases | Safety database | Locked extraction | Brand/batch completeness; duplicates |
| Trials | Clinical data | Cumulative cut | Product version; ADA assay context |
| Observational studies | Epidemiology | Study-specific | Exposure misclassification; switching |
| Literature | Information science/medical | Search interval | Brand, biosimilar, target, device terms |
| Quality/manufacturing | Quality | Change/complaint period | Batch, comparability, distribution |
| Devices | Device vigilance/quality | Presentation/lot | Complaint-to-case linkage |
| Signals/risks | Safety science | Governance dates | Attribution level |
| Benefits | Clinical/medical | Indication-specific | Actual delivery and immunogenicity |
| Actions | Regulatory/governance | Current status | Owner, territory, product scope |
Every package should have an owner, definition, extraction date, version, quality check and limitation statement.
Cross-section reconciliation matrix
Use explicit bidirectional checks:
| Statement | Must reconcile with |
|---|---|
| Product scope | Title, Sections 1, 2, 5 and appendices |
| DLP and interval | Title, all tables, signal dates and late-breaking information |
| RSI version/change | Sections 4, 6, 16, 19 and appendix |
| Exposure total | Sections 5, 6, 16.4, 17 and 18 |
| Trial finding | Sections 7, 13, 15–18 |
| Signal status | Sections 14, 15, 16.2 and 19 |
| Risk classification | Sections 16.1, 16.3, 16.4, RMP and conclusion |
| Action | Sections 3, 16.5, 19 and regional appendix |
| Device or batch issue | Sections 3, 5, 6, 15, 16 and quality records |
| Benefit–risk conclusion | Executive summary, Sections 18 and 19 |
A discrepancy is not automatically an error. It may reflect interval versus cumulative scope, DLP versus finalisation date, or different regulatory functions. It must nevertheless be explained.
Medical-review questions
The medical reviewer should answer:
- What materially changed during the interval?
- Is each outcome medically defined?
- Is each numerator compatible with its denominator?
- Which evidence can estimate frequency, and which cannot?
- At what biological identity level is attribution supported?
- Are route, formulation, device and batch differences real or products of missing data?
- Are immunogenicity findings linked to assay context, exposure and clinical consequence?
- Are alternative causes and conflicting evidence treated fairly?
- Does new information change frequency, severity, affected population, preventability or mechanism?
- Are benefits characterised separately by indication?
- Could uncertainty reverse the benefit–risk conclusion?
- Does every action follow from evaluated evidence?
Final consistency test
Run the report through five passes.
Pass 1: structural completeness
Verify title page, executive summary, Sections 1–20, applicable subsections, appendices and regional content. “Not applicable” requires rationale where the format expects a section.
Pass 2: dataset integrity
Check DLP, interval/cumulative boundaries, extraction dates, MedDRA version, RSI version, duplicates, study cuts and product dictionaries.
Pass 3: biological attribution
For every important finding, test class, active substance, product, batch, manufacturing period, formulation, route, device, use process and patient/disease explanations. Record why levels were included or excluded.
Pass 4: analytical coherence
Trace important findings from source section to signal/risk evaluation, risk characterisation, benefit–risk and action. Check numerator/denominator compatibility and uncertainty.
Pass 5: editorial and governance integrity
Confirm definitions, abbreviations, table consistency, cross-references, approvals, decision records and version history. Ensure illustrative wording is not confused with a mandatory template.
Practical authoring sequence
- Freeze the scope, DLP and RSI.
- Build product and indication maps.
- Issue controlled data requests.
- Validate exposure methods and table shells.
- Draft factual Sections 1–14.
- Reconcile the signal inventory.
- Complete signal evaluations and risk-by-risk updates.
- Reconstruct Section 16.4 from cumulative evidence.
- Characterise benefits by indication.
- Conduct integrated benefit–risk workshops.
- Draft conclusions and actions.
- Write the executive summary last.
- Perform independent medical, statistical, regulatory and quality review.
- Resolve inconsistencies through documented governance.
- Approve and preserve the evidence trail.
Common article-wide failure modes
- treating interval case counts as the report's central result;
- fragmenting evidence into sections without synthesis;
- using sales exposure as an incidence denominator;
- losing brand, batch, route or device identity during aggregation;
- attributing a confirmed device failure to molecular inefficacy;
- inferring immunogenicity from an uninterpretable antibody result;
- describing a manufacturing difference without comparability context;
- copying the RMP safety list without PSUR-specific reconciliation;
- confusing seriousness with severity;
- presenting relative risk without absolute context;
- omitting conflicting evidence or estimate precision;
- applying one benefit–risk conclusion to clinically different indications;
- writing actions that cannot be traced to evaluated evidence.
These are illustrative quality failures, not reported inspection findings.
Key Takeaways
- The PBRER is a connected evidence and decision system, not a periodic case inventory.
- Every formal section has a distinct regulatory purpose, input boundary, analytical task and output.
- Biological identity must be preserved at class, active-substance, product, batch, formulation, route and device levels according to the question.
- A transparent unknown is preferable to inferred brand or batch information.
- Exposure estimates require compatible scope, explicit assumptions and appropriate precision.
- Summary tabulations describe reports; they do not establish incidence or causality.
- Immunogenicity requires assay, sample timing, drug concentration, exposure and clinical-outcome context.
- Quality, manufacturing, device and pharmacovigilance evidence must be connected without collapsing their different questions.
- Section 16.3 evaluates what new evidence changed; Section 16.4 reconstructs the cumulative risk profile.
- Risk characterisation must address frequency, comparative risk, patient impact, public-health impact, risk factors, exposure pattern, preventability, reversibility, mechanism and uncertainty.
- Benefit evaluation must remain indication- and population-specific.
- An integrated benefit–risk conclusion identifies decision-driving benefits, risks and uncertainties and leads to explicit actions.
- Final quality depends on cross-section reconciliation as much as on the accuracy of individual sections.
References
- International Council for Harmonisation. ICH E2C(R2): Periodic Benefit-Risk Evaluation Report. Final version, 17 December 2012. https://database.ich.org/sites/default/files/E2C_R2_Guideline.pdf.
- International Council for Harmonisation. ICH E2C(R2) Questions and Answers. Consult the current Efficacy guideline implementation material. https://www.ich.org/page/efficacy-guidelines.
- European Medicines Agency. Guideline on good pharmacovigilance practices: Module VII — Periodic safety update report (Rev. 1). EMA/816292/2011 Rev.1; legally effective 13 December 2013. https://www.ema.europa.eu/en/documents/scientific-guideline/guideline-good-pharmacovigilance-practices-gvp-module-vii-periodic-safety-update-report_en.pdf.
- European Medicines Agency. Explanatory Note to GVP Module VII. EMA/670256/2017 Rev.4; updated 22 May 2026. Available from the EMA PSUR roadmap and PSUR procedural pages. https://www.ema.europa.eu/en/events/psur-roadmap-joint-industry-assessor-training.
- European Medicines Agency. Questions and answers on periodic safety update report single assessment: guidance for assessors. EMA/518909/2016 Rev.1; updated 22 May 2026. https://www.ema.europa.eu/en/events/psur-roadmap-joint-industry-assessor-training.
- European Medicines Agency. GVP Product- or Population-Specific Considerations II: Biological medicinal products. EMA/168402/2014; legally effective 16 August 2016. https://www.ema.europa.eu/en/documents/scientific-guideline/guideline-good-pharmacovigilance-practices-gvp-product-or-population-specific-considerations-ii-biological-medicinal-products_en.pdf.
- European Medicines Agency. Periodic safety update reports: procedural information, questions and answers, and EU reference dates list. https://www.ema.europa.eu/en/human-regulatory-overview/post-authorisation/pharmacovigilance-post-authorisation/periodic-safety-update-reports-psurs.
- European Parliament and Council. Directive 2001/83/EC, as amended, Articles 107b–107g. https://eur-lex.europa.eu/legal-content/EN/TXT/?uri=CELEX:02001L0083-20220101.
- European Parliament and Council. Regulation (EC) No 726/2004, as amended, Article 28. https://eur-lex.europa.eu/legal-content/EN/TXT/?uri=CELEX:02004R0726-20220128.
- European Medicines Agency. GVP Module V: Risk management systems (Rev. 2). EMA/838713/2011 Rev.2. https://www.ema.europa.eu/en/documents/scientific-guideline/guideline-good-pharmacovigilance-practices-module-v-risk-management-systems-rev-2_en.pdf.
- European Medicines Agency. GVP Module XVI: Risk minimisation measures (Rev. 3) and Addendum II: Methods for evaluating effectiveness of risk minimisation measures. Legally effective 6 August 2024. Available from the EMA GVP collection.
- European Medicines Agency. Guideline on immunogenicity assessment of therapeutic proteins. Consult the current applicable revision. https://www.ema.europa.eu/en/immunogenicity-assessment-therapeutic-proteins-scientific-guideline.
- European Medicines Agency. Guideline on comparability of biotechnology-derived medicinal products after a change in the manufacturing process. Consult the current applicable revision.
- QPPV.com. GVP Module VII: Writing the PSUR Safety Evaluation.
- QPPV.com. GVP Product- or Population-Specific Considerations II: Biological Medicinal Products.
- QPPV.com. How to Develop and Maintain RMPs for Biological Medicinal Products.
- QPPV.com. Signal Management for Biological Medicinal Products.
- QPPV.com. ICSR Management for Biological Medicinal Products.
Regulatory Note
This article is an educational technical interpretation of the PBRER/PSUR framework. It does not replace current EU legislation, ICH E2C(R2), EU GVP Module VII, current EMA explanatory and procedural material, the applicable EU reference-dates list, submission instructions, product information, risk-management plan or product-specific competent-authority conditions. The fictional mAb-X dossier and all illustrative values demonstrate analytical method; they do not represent an authorised product, regulatory precedent, expected safety profile or mandatory wording.