Lebrikizumab: Classification, History, Mechanism of Action, Safety and Pharmacovigilance
- Lebrikizumab: Classification, History, Mechanism of Action, Safety and Pharmacovigilance
- Multidimensional classification
- Molecular identity and mechanism
- Development and regulatory context
- Clinical safety architecture
- High-value event follow-up
- Pharmacovigilance case assessment
- Signal detection and aggregate review
- Periodic benefit-risk evaluation
- Risk management and operational controls
- Potential failure modes
- Inspection and governance perspective
- Practical checklist
- Key Takeaways
- References
- Regulatory Note
Lebrikizumab is a humanised IgG4 monoclonal antibody directed against IL-13. Its pharmacological effect is binding IL-13 and reducing signalling through the IL-4 receptor alpha/IL-13 receptor alpha 1 complex. This places the substance within the interleukin-13 inhibitor class and makes safety surveillance dependent on both the intended pathway effect and the patient’s underlying disease.
The pharmacovigilance question is broader than whether an event is listed in a label. A useful assessment asks what biological function changed, when exposure occurred, what other treatments were present, which disease processes could produce the same finding and whether the event persisted after treatment was held.
Multidimensional classification
| Axis | Lebrikizumab | PV significance |
|---|---|---|
| Molecular class | humanised IgG4 monoclonal antibody | A biological medicinal product with substance- and product-specific quality attributes |
| Target | IL-13 | Identifies the pathway whose modulation explains plausible benefit and harm |
| Functional class | interleukin-13 inhibitor | Helps define event phenotypes and differential diagnoses |
| Route | subcutaneous injection | Shapes administration chronology and traceability |
| Clinical context | moderate-to-severe atopic dermatitis in selected adults and adolescents in authorised settings; age, topical treatment and regional labels govern use | Indication and co-therapy alter background risk and benefit |
| Product category | Biological medicinal product | Presentation, batch, storage and preparation may matter in investigations |
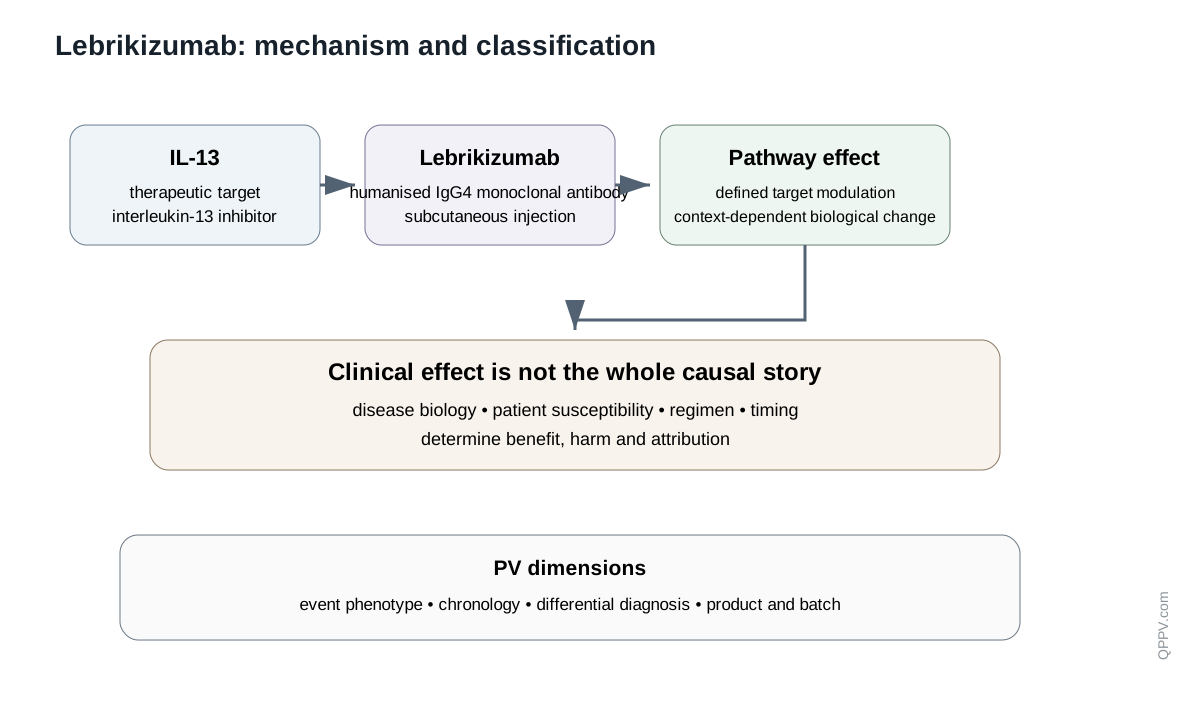
Figure 1. The target and pathway effect provide the scientific anchor; disease, regimen, chronology and product identity determine pharmacovigilance interpretation.
Molecular identity and mechanism
Lebrikizumab does not act as a nonspecific immune stimulus. It binds a defined target and changes signalling in a particular biological compartment. The downstream result depends on target expression, target occupancy, immune reserve, disease activity and concurrent treatment.
The antibody format is relevant but not sufficient to explain safety. Fc characteristics, glycosylation, aggregation, charge variants, concentration, container closure and other critical quality attributes can influence product behaviour and immunogenicity. The case should preserve the exact product and presentation where available.
Mechanism-led safety hypothesis
A mechanism-led review should:
- identify the target and its normal physiological function;
- describe the intended pharmacological change;
- identify tissues or processes that may be affected;
- define clinical phenotypes that support or weaken the hypothesis;
- distinguish treatment-emergent findings from disease-related background events.
For Lebrikizumab, this points toward conjunctivitis and other ocular effects, keratitis, eosinophilia, herpes-virus infection, hypersensitivity, injection-site reactions and helminth-infection considerations. It does not prove causality in an individual case. It defines what information should be collected and what signals should be watched.
Development and regulatory context
Lebrikizumab was developed as a targeted biological therapy in a defined disease and treatment context. The authorised programme is not identical in every jurisdiction. Current regional product information controls the applicable indication, population, dose, contraindications, warnings, monitoring and combination requirements.
For PV operations, the authorised context should remain visible in intake, case processing, medical review, signal detection, periodic reporting, risk-management documentation and quality oversight. If indication or treatment intent is missing, a later reviewer may be unable to separate disease morbidity from treatment-related change.
The references in the final chunk are regulatory or scientific anchors. Statements about authorised use are jurisdiction-specific. Operational recommendations are recommendations and should be mapped to local procedures and requirements.
Clinical safety architecture
The safety profile of Lebrikizumab reflects three interacting layers:
| Layer | Contribution | PV implication |
|---|---|---|
| Direct pharmacology | Biological function changed by IL-13 modulation | Follow pathway-specific findings and laboratory changes |
| Host susceptibility | Age, infection history, immune status, organ reserve and comorbidity | Preserve baseline status and relevant risk factors |
| Treatment environment | Disease severity, procedures, co-medicines and prior therapies | Reconstruct the complete regimen rather than attributing by name |
The same symptom can arise from more than one layer. Fever may be infection, cytokine release, tumour activity or an administration reaction. A laboratory abnormality may be pharmacodynamic, organ injury, disease progression or a concomitant effect. The narrative should retain evidence needed to distinguish these possibilities.
High-value event follow-up
| Concern | Information that can change assessment |
|---|---|
| Serious or opportunistic infection | Site, organism, cultures, imaging, antimicrobials, immune status and outcome |
| Infusion or injection reaction | Product and batch, administration chronology, rate or device, vital signs, treatment and rechallenge |
| Organ-specific injury | Baseline and serial tests, imaging or functional testing, competing causes, treatment and persistence |
| Haematological or inflammatory change | Baseline counts or markers, trend, symptoms, disease activity and clinical consequence |
| Hypersensitivity or immunogenicity | Timing, phenotype, anti-drug antibody testing where indicated, repeat exposure and outcome |
| Lack of effect or rebound | Schedule, adherence, interruptions, disease measurements and switching |
| Product-quality concern | Presentation, batch, expiry, storage, preparation, administration system and associated cases |
For Lebrikizumab, follow-up should be event-led. A targeted request asks for data that can change seriousness, causality, expectedness, clinical management, signal interpretation or traceability.
Pharmacovigilance case assessment
A complete reconstruction follows the chain:
- why treatment was started and what outcome was intended;
- exact exposure dates, dose, route, formulation, batch and setting;
- all concomitant medicines, recent procedures and previous biological therapies;
- event onset, evolution, objective findings, treatment and outcome;
- alternative causes and evidence supporting or weakening each;
- dechallenge, rechallenge, interruption, continuation or switching;
- whether the event was delayed, recurrent or multi-system.
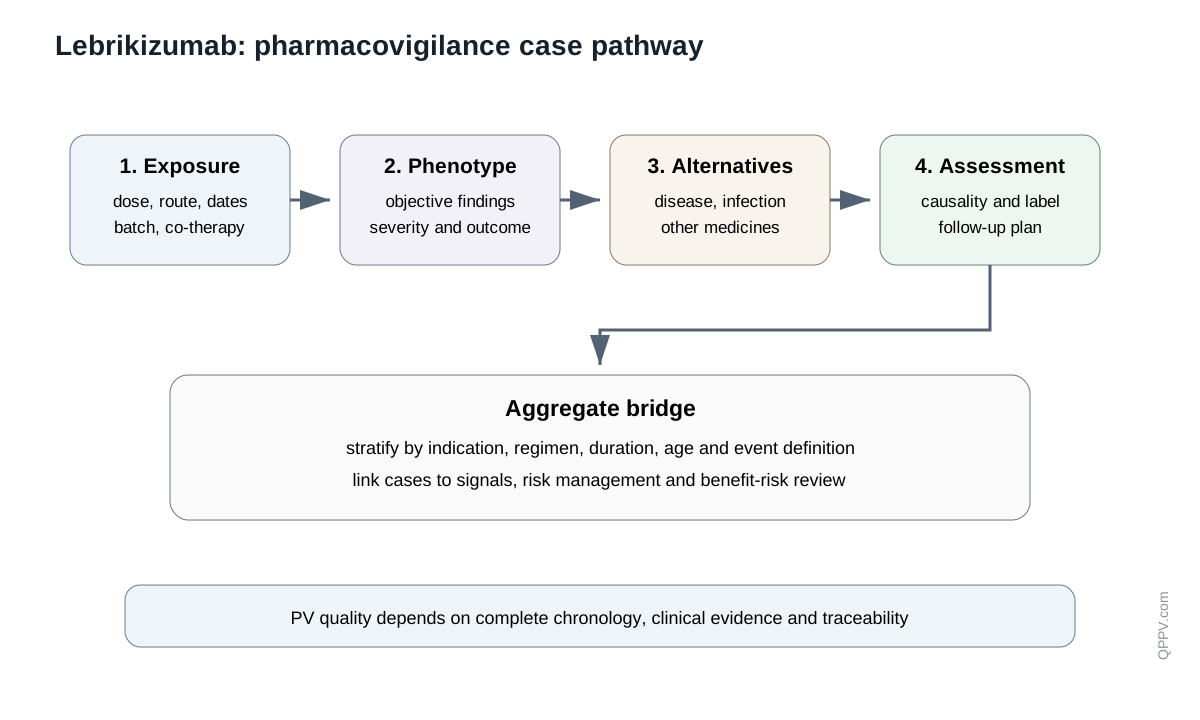
Figure 2. Individual cases become useful for aggregate surveillance when exposure, phenotype, alternatives and assessment are connected in a traceable chronology.
Causality without shortcuts
Temporal association is necessary but rarely sufficient. A plausible mechanism strengthens a hypothesis, while a strong competing cause weakens it. Dechallenge can be confounded by treatment for the event. Rechallenge may provide information but may be clinically inappropriate and should not be treated as a routine test.
For Lebrikizumab, reviewers should record evidence rather than force a binary answer too early. Terms such as “immune-mediated,” “pathway-related,” “treatment failure” or “administration reaction” should be supported by findings and not used as unexplained labels. Relevant alternatives include atopic dermatitis activity, bacterial or viral skin infection, ocular surface disease and concomitant topical or systemic therapy.
Signal detection and aggregate review
Signal detection should preserve strata that can alter event rate or meaning. Consider indication, disease severity, treatment line, monotherapy or combination, duration, age, baseline organ function, prior therapy and region.
Preferred-term review is not the end of the analysis. A cluster of terms may represent one syndrome, while one term may include several mechanisms. Align case definitions, medical review, laboratory confirmation, exposure denominators and outcome severity before drawing a conclusion.
A signal is a hypothesis requiring evaluation. Compare observed cases with background disease rates, known class effects, concomitant medicines, reporting stimulation, clinical-practice changes and product or batch information. State what is known, uncertain and proportionate to the evidence.
Periodic benefit-risk evaluation
Periodic reporting should connect identified and potential risks with the actual benefit population. Benefit may be response, disease control, prevention of progression, preservation of organ function or another endpoint defined by the authorised setting.
For Lebrikizumab, ask whether serious events cluster by indication, age or treatment phase; whether laboratory changes become clinically meaningful; whether toxicity is delayed or persistent; whether combinations change phenotype; and whether cases are complete enough to support a conclusion. Absence of reports is not proof of absence, especially where an event is hard to recognise or the product is used in a specialised population.
Risk management and operational controls
Current regional product information and applicable pharmacovigilance legislation establish the regulatory baseline. The following operational recommendations support an effective system:
- structured fields for indication, treatment intent, line and combination;
- exact dose, route, administration date, presentation and batch where available;
- event-specific follow-up reflecting IL-13 biology and the disease;
- baseline and serial laboratory, imaging or functional findings when relevant;
- documented competing causes, medical reasoning and review decisions;
- monitoring for delayed events after interruption or discontinuation;
- reconciliation with quality complaints, medical-information contacts and distribution records;
- an evidence trail from source report to case narrative, coding, assessment and aggregate action.
These controls support compliance and good practice, but the exact workflow, field design and ownership model remain system decisions unless a specific requirement makes them mandatory.
Potential failure modes
The following are illustrative scenarios, not published inspection findings:
- A case is coded from a symptom without recording objective findings that distinguish disease from treatment effect.
- A serious infection is assessed without reviewing baseline immune status, procedures or concomitant immunosuppression.
- An interruption is treated as a complete dechallenge even though biological effect may persist.
- A laboratory or imaging finding is counted as a signal without assessing clinical consequence.
- A product-quality cluster cannot be investigated because presentation, batch, storage or administration details were not captured.
- A combination regimen is collapsed into one exposure field, preventing attribution and subgroup analysis.
- A periodic report pools populations whose background risk and treatment intent differ.
- Delayed or recurrent events are missed because follow-up ends at the next scheduled dose.
Inspection and governance perspective
An effective PV system should show that Lebrikizumab cases are recognised, followed up, medically assessed and used in aggregate review according to their scientific context. Evidence may include case-processing guidance, targeted questionnaires, medical-review criteria, signal-detection methods, periodic reports, reconciliation records, product dictionaries, batch-investigation records and escalation decisions.
The governance test is not whether a procedure exists. It is whether the procedure produces reliable evidence. If serious infections, imaging findings or administration events require follow-up, the system should demonstrate that follow-up was sent, evaluated and reflected in the case. If signal detection is indication-specific, the database and outputs should make that stratification possible.
Practical checklist
For a Lebrikizumab case or aggregate review, confirm:
- exact substance, product, presentation, dose, route, date and batch where available;
- authorised indication or clinical-use context and treatment intent;
- complete co-medication, prior-therapy and recent-procedure history;
- event chronology relative to each treatment and disease milestone;
- objective findings, severity, treatment and outcome;
- differential diagnosis and evidence supporting the medical assessment;
- dechallenge, rechallenge, interruption, persistence or recurrence;
- appropriate coding and event grouping for signal detection;
- traceability to product-quality, distribution and administration information;
- preservation of the relevant benefit population in aggregate review.
Key Takeaways
Lebrikizumab is a humanised IgG4 monoclonal antibody directed against IL-13 and administered by subcutaneous injection. Its principal effect is binding IL-13 and reducing signalling through the IL-4 receptor alpha/IL-13 receptor alpha 1 complex. That mechanism explains why case assessment must connect molecular biology with patient susceptibility, disease context and treatment chronology.
The central PV risk is not simply a list of reactions. It is the possibility that pathway-specific harm, disease morbidity, combination toxicity, administration events and product-quality issues will be conflated. High-quality surveillance depends on targeted follow-up, explicit differential diagnosis, indication-aware signal detection and reliable traceability.
References
- Current regulatory product information for Lebrikizumab. https://www.ema.europa.eu/en/medicines/human/EPAR/ebglyss
- Current product information or prescribing material for Lebrikizumab. https://ebglyss.lilly.com/
- Scientific or regulator-hosted evidence relevant to Lebrikizumab. https://pubmed.ncbi.nlm.nih.gov/?term=lebrikizumab+atopic+dermatitis
- European Medicines Agency. Good pharmacovigilance practices, Module I. https://www.ema.europa.eu/en/human-regulatory-overview/research-development/pharmacovigilance-research-and-development/good-pharmacovigilance-practices
- European Medicines Agency. GVP Module V: Risk management systems. https://www.ema.europa.eu/en/documents/scientific-guideline/guideline-good-pharmacovigilance-practices-module-v-risk-management-systems-rev-2_en.pdf
- European Medicines Agency. GVP Module IX: Signal management. https://www.ema.europa.eu/en/documents/scientific-guideline/guideline-good-pharmacovigilance-practices-gvp-module-ix-signal-management-rev-1_en.pdf
Regulatory Note
Authorised indications, dosing, contraindications, monitoring, warnings and combination requirements vary by jurisdiction and may change. This article explains scientific and pharmacovigilance principles and does not replace current regional product information. Regulatory requirements and operational recommendations are intentionally distinguished. Product information for this article was checked against current regulator or regulator-hosted sources in September 2026.