What Is a QPPV?
A qualified person responsible for pharmacovigilance, usually abbreviated to QPPV, is the individual whom a marketing authorisation holder must have permanently and continuously at its disposal to take responsibility for the establishment and maintenance of the pharmacovigilance system in the European Union.[1,2] The title is compact, but it contains three ideas that need to be separated before the role can be understood.
A marketing authorisation is the regulatory permission that allows a medicinal product to be placed on a market. The legal entity holding that permission is the marketing authorisation holder or MAH. Pharmacovigilance is the science and set of activities concerned with detecting, assessing, understanding and preventing adverse effects or other medicine-related problems. A pharmacovigilance system is the organised network of people, processes, data, technology and governance through which the MAH performs those activities.
The QPPV sits within that system as its continuously available expert point of oversight. The QPPV is not the holder of the marketing authorisation, does not replace the company’s governing body and does not personally perform every pharmacovigilance task. The MAH remains responsible for compliance with its legal obligations. The QPPV must nevertheless be placed in a position where important safety information reaches one identifiable, appropriately qualified person who can understand its significance, require appropriate evaluation and influence action across organisational boundaries.[2,3]
This distinction is the foundation of the role:
The MAH owns the legal responsibility; the QPPV provides identifiable, continuous and expert oversight of the system through which that responsibility is discharged.
Why the Role Exists
Medicinal-product safety cannot be managed by one department working in isolation. A report from a patient may first reach a call centre. A clinical study may identify an unexpected risk. Manufacturing changes may alter product characteristics. A commercial partner may hold safety information in another country. A signal-analysis team may detect a pattern across many individual reports. Regulatory affairs may receive a new condition imposed on an authorisation. Quality personnel may discover that cases were transmitted late.
Each item may appear in a different system and under different management. Yet the safety question is often larger than the function in which the information first appeared. The organisation therefore needs a person with sufficient visibility across the whole pharmacovigilance system and across the safety profiles of the medicines covered by it.
An analogy can clarify the design without replacing the regulatory terminology. The QPPV resembles the person responsible for maintaining an air-traffic control view rather than the pilot of every aircraft. Individual specialists perform particular operations, but someone must be able to see how the movements interact, recognise when information changes the overall risk picture and ensure that an appropriate response is coordinated. The analogy has limits: the QPPV works within corporate governance and the MAH remains legally responsible. Its value is simply to show why oversight is different from personally performing every task.
The Legal Architecture
The legal requirement begins with Directive 2001/83/EC. Article 104 requires the MAH to operate a pharmacovigilance system and to have permanently and continuously at its disposal an appropriately qualified QPPV who resides and operates in the Union.[1] The European Economic Area extends relevant EU medicines arrangements to participating EEA states, which is why operational language commonly refers to an EU/EEA QPPV.
Commission Implementing Regulation (EU) No 520/2012 adds requirements concerning competence and organisational support. The MAH must ensure that the QPPV has adequate theoretical and practical knowledge for pharmacovigilance. If the QPPV has not completed the specified basic medical training, the MAH must ensure assistance by a medically trained person and document that assistance. The Regulation also requires duties and hierarchical relationships to be defined through job descriptions and an organisational chart.[2]
The Good Pharmacovigilance Practices, or GVP, then explain how the legal framework should operate. GVP Module I describes the QPPV’s system-level responsibilities, necessary authority and access to information. GVP Module II connects the QPPV to the pharmacovigilance system master file, or PSMF, which is the controlled description of the pharmacovigilance system.[3,4]
These sources do not all have the same legal character. The Directive and directly applicable Regulation establish binding requirements. GVP provides regulatory guidance for implementing those requirements. An organisation’s procedures translate the framework into its own operating model, but an internal procedure cannot reduce the underlying obligation.
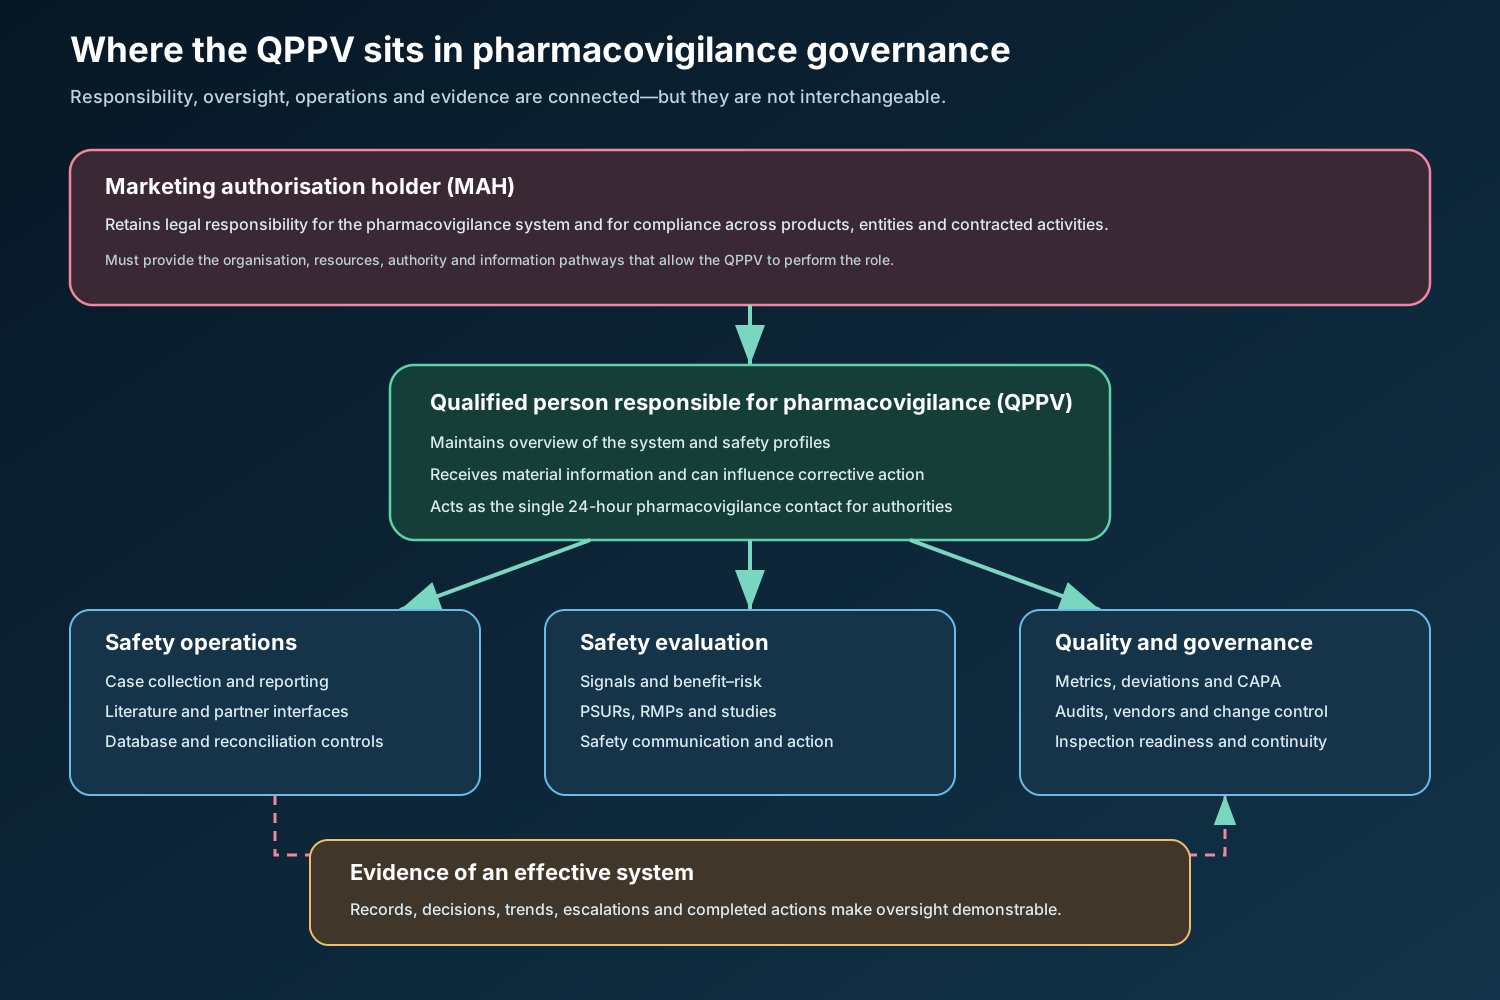
Figure 1. The MAH retains legal responsibility, while the QPPV maintains system and product-safety overview across operations, evaluation and quality governance. Records and completed actions provide evidence that this oversight operates in practice.
What the Word “Qualified” Means
“Qualified” does not mean that EU law prescribes one universal degree, professional title or career route for every QPPV. The applicable standard is functional: the person must have adequate theoretical and practical pharmacovigilance knowledge for the role and must be appropriately qualified for the system and product portfolio concerned.[2,3]
The distinction matters because pharmacovigilance requires several forms of competence:
- clinical and scientific interpretation of safety information;
- understanding of the applicable regulatory framework;
- knowledge of pharmacovigilance processes and data flows;
- ability to recognise system and compliance risk;
- authority to communicate across functions and escalate concerns;
- judgement under uncertainty;
- and sufficient familiarity with the MAH’s products and operating model.
A QPPV need not personally be the organisation’s leading expert in every therapeutic area, database or statistical method. The role must instead have access to appropriate expertise and be able to integrate specialist conclusions into a system-level view. Where medical assistance is legally required because the QPPV lacks the specified basic medical training, that arrangement must be real and documented rather than nominal.[2]
The separate article EU QPPV Requirements examines qualification, residence and formal regulatory requirements in greater detail. The present article focuses on what the role means within the pharmacovigilance system.
From Responsibility to Oversight
The word responsible in the QPPV title can be misunderstood in two opposite ways. One interpretation makes the QPPV personally accountable for every action taken by every employee and service provider. The other reduces the role to receiving reports and signing documents prepared by others. Neither interpretation describes effective pharmacovigilance governance.
The MAH remains the regulated legal entity. It must establish the pharmacovigilance system, provide sufficient competent personnel, maintain its quality system and meet the obligations attached to its marketing authorisations.[1,2] The QPPV has a defined responsibility within that corporate framework: maintaining overview of the functioning of the pharmacovigilance system and of the safety profiles of the products covered by it.[3]
Oversight means obtaining sufficient information to understand performance and risk, applying appropriate judgement, influencing decisions, and following important matters through to resolution. It is not equivalent to routine line management. A QPPV may oversee a case-processing system without supervising every case processor, but cannot do so credibly without information about case volumes, quality, reporting compliance, significant deviations and unresolved risks.
This produces four connected requirements:
- Visibility: material information must reach the QPPV.
- Interpretability: the information must be sufficiently clear and contextualised to support judgement.
- Influence: the QPPV must be able to request evaluation, escalation or change.
- Closure: the QPPV must receive evidence showing what was decided, what was completed and whether the response was effective.
Overview of Product Safety
A safety profile is the organised understanding of a medicinal product’s important risks, potential risks, uncertainties and other safety characteristics in the context of its use. It is not merely a list of reported adverse reactions. The profile develops from individual case safety reports, clinical studies, scientific literature, epidemiological data, class knowledge, non-clinical findings, medication errors, exposure information and regulatory assessments.
The QPPV should therefore be aware of emerging safety concerns and of information capable of changing the benefit–risk evaluation of products covered by the system.[3] A benefit–risk evaluation compares the favourable effects of a medicine with its risks in the authorised conditions of use. It is a structured scientific and regulatory judgement, not a numerical subtraction of adverse events from treatment successes.
The QPPV does not independently reproduce every signal assessment or clinical review. Instead, the role needs enough access to the underlying evidence and specialist reasoning to determine whether conclusions are coherent, whether uncertainty has been represented appropriately and whether further action is required.
Authority Is More Than Seniority
A senior title does not by itself create effective authority. For the QPPV, authority must operate through the organisation’s actual decision pathways. GVP Module I describes authority over the pharmacovigilance system and the PSMF that should allow the QPPV to implement changes to the system and contribute to risk-management planning and regulatory action.[3]
In practice, this means the governance model should answer questions such as:
- Can the QPPV obtain information from any relevant part of the organisation?
- Can the QPPV require a safety issue to be assessed?
- Can the QPPV escalate a concern beyond the management line that generated it?
- Can the QPPV request an audit where appropriate?
- Is the QPPV involved early enough in acquisitions, divestments and product transfers to assess pharmacovigilance consequences?
- Can the QPPV influence contractual provisions governing safety information?
- Is disagreement documented and escalated to a body with authority to decide?
Authority does not mean that every recommendation must automatically become the corporate decision. Some decisions require accountable governance bodies and input from medical, regulatory, quality, legal, supply or executive functions. The essential control is that the QPPV’s assessment is heard at the right level, disagreements remain visible and the resulting decision has a traceable rationale.
Access to Information
GVP Module I expects the MAH to establish mechanisms through which the QPPV receives relevant information and can access information considered necessary.[3] This includes more than adverse-event reports. Depending on the organisation, relevant information can arise from:
| Information source | Why it can matter to the QPPV |
|---|---|
| Individual case safety reports | May reveal a new clinical pattern, reporting failure or urgent case |
| Signal-management outputs | Show whether new or changing safety issues require action |
| Clinical and non-interventional studies | May alter the evidence supporting benefit or risk |
| PSURs and benefit–risk evaluations | Integrate cumulative evidence and proposed conclusions |
| Risk management plans | Define important risks, uncertainties and planned controls |
| Product complaints and quality defects | May connect manufacturing or device problems to patient harm |
| Regulatory correspondence | May impose commitments, deadlines or changes |
| Compliance metrics and deviations | Show whether the pharmacovigilance system is performing reliably |
| Audit reports and CAPA | Identify weaknesses and the actions intended to correct them |
| Contracts and partner exchanges | Define where safety information originates and how it moves |
| Organisational and portfolio changes | Can alter workload, interfaces, responsibilities and system scope |
Access must be timely enough for the information to remain actionable. A monthly report may be appropriate for a stable performance measure but inadequate for an emerging safety concern requiring immediate evaluation. The organisation should therefore distinguish routine periodic information from event-driven escalation.
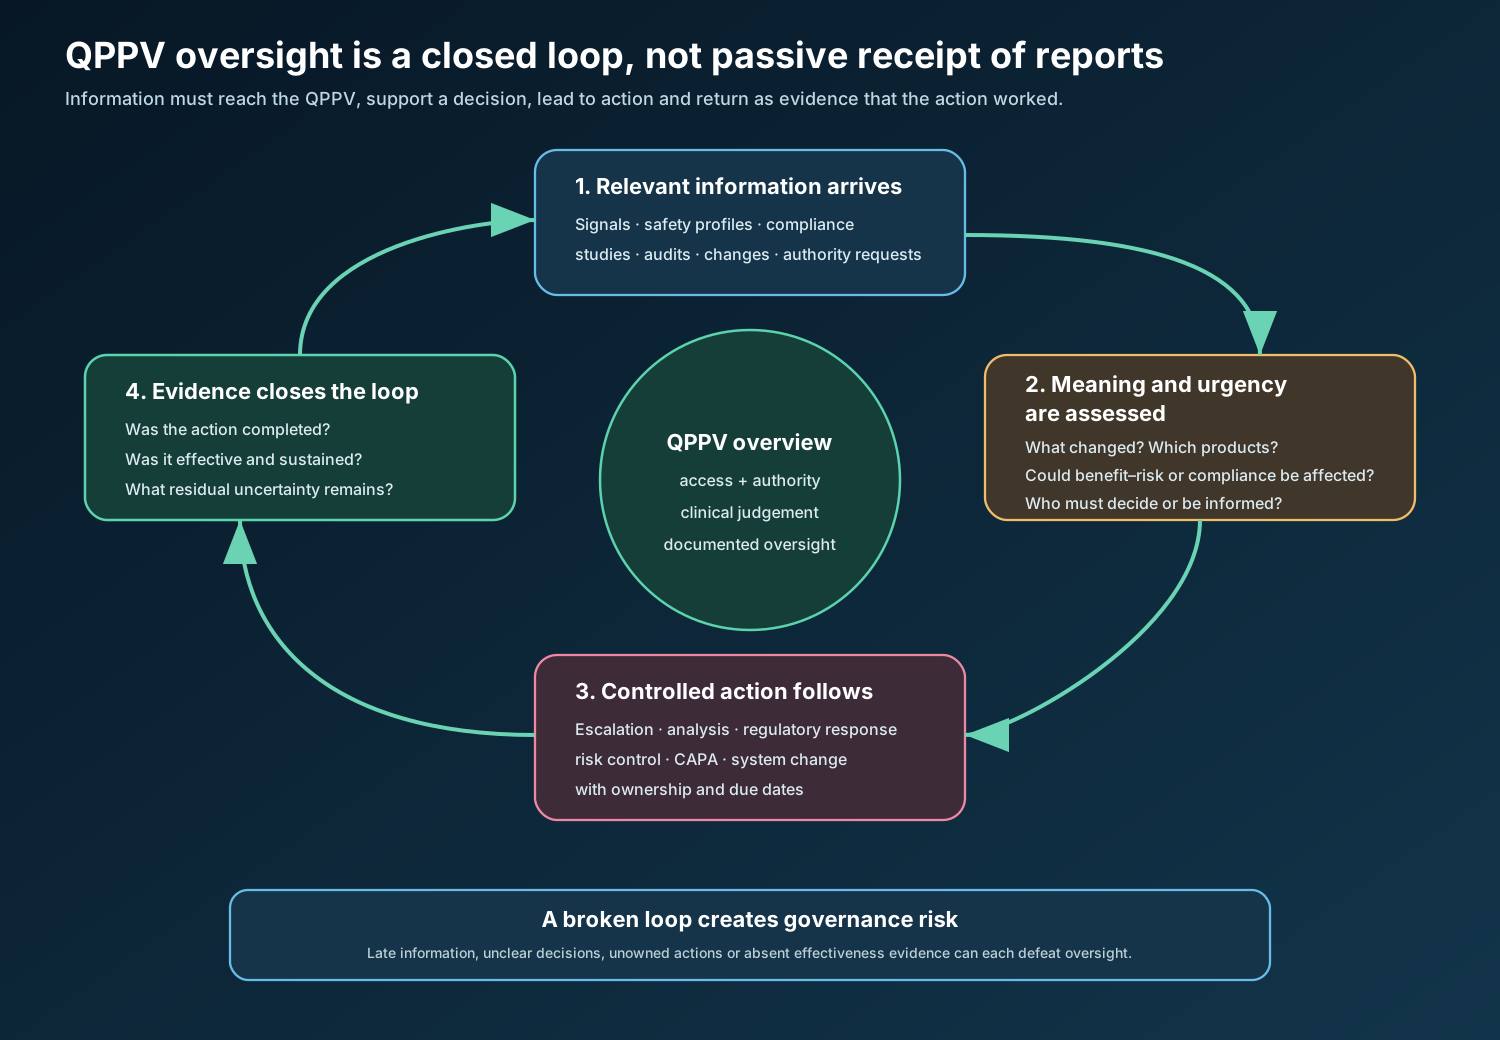
Figure 2. Effective oversight forms a closed loop. Information must be assessed, translated into controlled action and followed by evidence of completion and effectiveness. Failure at any point can leave the QPPV apparently informed but unable to demonstrate meaningful oversight.
Permanent and Continuous Availability
The legal phrase permanently and continuously at its disposal describes the MAH’s obligation to maintain uninterrupted access to the QPPV function.[1] GVP Module I further describes the QPPV as the single pharmacovigilance contact point for competent authorities and the Agency on a 24-hour basis and as a contact point for pharmacovigilance inspections.[3]
This does not mean one person must remain awake and personally answer every communication at all hours. It means the organisation needs a reliable continuity arrangement through which an urgent authority contact or safety matter can reach an appropriately prepared response pathway at any time. Deputies, on-call mechanisms, current contact details, access to systems and documented handovers may all contribute to that arrangement.
The continuity model must preserve rather than fragment oversight. A deputy should know when the arrangement activates, what authority accompanies it, which matters require immediate action and how information returns to the QPPV. The specialist article Deputy QPPV addresses those controls in detail.
The QPPV as Regulatory Contact
The QPPV provides a single expert pharmacovigilance contact for EU competent authorities and EMA.[3] This enables a regulator to reach someone capable of understanding both a product-safety issue and the system through which the MAH is managing it.
Being the contact point does not mean that all regulatory communication must be drafted or transmitted personally by the QPPV. Regulatory-affairs personnel and specialist pharmacovigilance teams may manage routine submissions and correspondence. The QPPV nevertheless needs visibility of material requests, conclusions, commitments and unresolved issues, together with the ability to ensure that the response is complete and appropriately supported.
A Member State may also require nomination of a national pharmacovigilance contact reporting to the QPPV.[1] Such a contact supports national accessibility; it does not replace the EU QPPV’s system-level role.
Relationship With the PSMF
The pharmacovigilance system master file is the controlled description of the pharmacovigilance system used for one or more authorised medicinal products. It describes how the system is organised and points to supporting information about responsibilities, processes, data sources, computerised systems, delegated activities, performance and quality management.[4]
The PSMF can be compared to an evidence-supported map of the system. A map is useful only if it represents the territory accurately. In the same way, a PSMF that describes procedures no longer followed, vendors no longer used or responsibilities that have changed cannot support effective oversight merely because it is complete as a document.
The QPPV must have access to the PSMF and authority over it and should be informed of changes relevant to the pharmacovigilance system.[3,4] This does not require the QPPV to perform every document-maintenance task. It requires the QPPV to be able to understand the system described, identify material inaccuracies or gaps, and influence correction.
The PSMF also makes the QPPV role inspectable. It should allow an inspector to understand who the QPPV is, what the role covers, how availability is maintained, which tasks have been delegated and how the QPPV exercises authority and obtains information. The articles What Is a PSMF? and PSMF Governance and Inspection Findings develop those subjects separately.
Delegation and Outsourcing
A large pharmacovigilance system depends on distributed work. Case processing may be performed by regional teams or vendors. Signal analyses may be led by safety physicians. Regulatory submissions may be transmitted by operations specialists. Literature searches, medical information and patient-support programmes may involve contracted providers.
The QPPV can delegate specific tasks to appropriately qualified and trained individuals, but delegation does not eliminate the QPPV’s system overview or product-safety overview.[3] The distinction is between delegating performance of a task and abandoning oversight of its consequences.
A sound delegation arrangement identifies:
- the task and its boundaries;
- the person or role receiving it;
- the competence required;
- the authority accompanying the task;
- the information and systems needed;
- escalation criteria;
- continuity during absence;
- records generated;
- and how the QPPV remains informed.
Outsourcing creates a related but separate relationship. A vendor may contractually perform pharmacovigilance activities, but the MAH cannot contract away its legal responsibility. The QPPV therefore needs visibility of material vendor performance, deviations, audit results, corrective actions and changes capable of affecting the system.
This is why the Safety Data Exchange Agreement, Vendor Oversight and Selecting and Appointing a QPPV articles sit beside this conceptual introduction rather than inside it.
How the Role Operates Across the Product Lifecycle
The QPPV role is continuous, but its emphasis changes as products and systems change.
Before and during authorisation
The applicant must establish the pharmacovigilance system that will support the authorised product. The QPPV needs sufficient familiarity with the proposed system, product safety profile, risk-management arrangements and important interfaces to perform the role when the authorisation becomes effective.
Routine post-authorisation operation
During stable operation, the QPPV’s overview is supported by information such as signal outputs, aggregate assessments, risk-management activities, compliance data, deviations, audit findings and regulatory correspondence. Routine oversight should create familiarity with normal performance so that meaningful change becomes recognisable.
Emerging safety concerns
When new information could materially affect benefit–risk or public health, the system must move from routine reporting to timely assessment and governance. The QPPV should understand the evidence, affected products and populations, uncertainty, proposed regulatory communication and planned risk-control actions.
Organisational and product change
Acquisitions, divestments, licensing arrangements, new indications, new formulations, database migrations, vendor changes and reorganisations can alter safety-information pathways. GVP Module I advises early QPPV involvement in portfolio expansion so the impact on the pharmacovigilance system and contractual arrangements can be assessed.[3]
System failure and recovery
Where a deviation affects reporting, signal management, risk minimisation or another critical activity, the QPPV needs information about scope, safety impact, interim controls, root cause, corrective and preventive action and effectiveness verification. Awareness of an open issue is not equivalent to assurance that it has been contained and corrected.
What the QPPV Is Not
Clear boundaries help a new reader understand the role.
| The QPPV is not… | The necessary distinction |
|---|---|
| The MAH | The company or other legal entity remains the marketing-authorisation holder and retains legal responsibility |
| The qualified person for batch certification | That manufacturing role concerns certification and release of medicinal-product batches; it is a different legal function |
| The head of every PV team | Organisational reporting lines vary; QPPV authority and access must work regardless of line-management structure |
| The processor of every safety case | Case handling can be delegated, but system performance and significant safety implications must remain visible |
| The sole benefit–risk decision-maker | Decisions may require multidisciplinary governance, but the QPPV must be able to contribute and escalate |
| A substitute for adequate staffing | Appointment of a QPPV does not compensate for insufficient competent personnel or defective systems |
| A ceremonial signatory | A signature without information, judgement, authority and follow-through does not demonstrate oversight |
The QPPV is also not automatically the same person as a local safety officer, a UK national contact person, a safety-system owner or a medical director. One individual may hold multiple roles, but each role’s scope, authority, potential conflicts and continuity arrangements should remain explicit.
From Information to Evidence of Oversight
An organisation demonstrates QPPV oversight through connected evidence rather than through a single certificate or job description. Useful evidence may include:
- current role and delegation records;
- documented induction and continuing competence;
- agendas and minutes showing participation in relevant governance;
- safety and compliance reports supplied to the QPPV;
- decisions, challenges and escalations;
- evidence of input to risk-management and regulatory action;
- audit notifications and follow-up;
- records of system and portfolio changes;
- documented availability and deputy arrangements;
- and confirmation that important actions were completed and evaluated.
No universal meeting frequency, dashboard or committee structure is mandated for every organisation. The appropriate model depends on product risk, portfolio size, organisational complexity, geographic reach and the nature of outsourced activities. Recommended practice should therefore be proportionate and justified rather than presented as a fixed legal formula.
Illustrative Oversight Scenarios
A late-reporting trend
A dashboard shows that expedited reports are increasingly late. Merely forwarding the dashboard to the QPPV establishes receipt, not effective oversight. A meaningful response would establish the scale and cause, assess any regulatory or patient-safety consequence, implement interim controls, assign corrective action and return evidence of effectiveness.
A new licensing partner
A new partner will receive adverse-event information in several countries. The QPPV does not need to negotiate every commercial clause, but should have timely access to the pharmacovigilance provisions and be able to challenge unclear responsibilities, unsuitable exchange timelines or incomplete reconciliation arrangements.
Disagreement about a safety concern
A safety team considers an emerging concern urgent while another function believes that action should wait. Effective governance records the evidence and uncertainty, obtains the QPPV’s assessment, identifies the accountable decision-maker and documents the conclusion and follow-up. Agreement is not the control; a visible and scientifically defensible decision pathway is.
How an Inspector Can Evaluate the Role
An inspection does not establish effective QPPV oversight merely by confirming that a named individual exists. The relevant question is whether the pharmacovigilance system enables that individual to perform the role and whether the evidence shows that the arrangement works.
An inspector may therefore trace a real issue through the oversight loop:
- When did information first become available?
- Through which process did it reach the QPPV?
- What context accompanied it?
- What assessment or challenge occurred?
- Who made the resulting decision?
- What action was assigned?
- How was completion verified?
- Was effectiveness evaluated?
- Could the same pathway operate outside normal working hours?
The answers may be found across governance minutes, safety assessments, correspondence, dashboards, deviation records, CAPA documentation and system-access evidence. The purpose is not to accumulate documents. It is to determine whether the role is connected to the actual operation of the system.
Potential failure modes include delayed escalation, incomplete portfolio visibility, nominal authority without an effective escalation route, insufficient access to vendor information, unclear delegation, outdated contact details, weak deputy arrangements and actions that remain open without effectiveness evidence. These are analytical categories and illustrative inspection questions, not assertions that a particular authority has reported a finding against a particular organisation.
A Practical Test of QPPV Oversight
A reader can test any QPPV arrangement using six questions.
| Question | What a credible answer should establish |
|---|---|
| What does the QPPV cover? | The relevant pharmacovigilance system, legal entities, products, territories and important interfaces |
| What reaches the QPPV? | Defined routine information and event-driven escalation from all material sources |
| What can the QPPV do? | Obtain information, challenge conclusions, request evaluation or audit, influence change and escalate |
| How is continuity maintained? | Working availability, deputies, on-call access, handover and current authority-contact details |
| How are decisions followed? | Ownership, due dates, completion evidence and effectiveness review |
| How can this be demonstrated? | Consistent records connecting information, judgement, decision and action |
A weakness in one answer does not automatically prove that the whole pharmacovigilance system is ineffective. It identifies an area that needs closer assessment. For example, absence from one meeting may be immaterial if the QPPV received the necessary information through another controlled route. Conversely, attendance at every meeting may provide little assurance if decisions and follow-up cannot be reconstructed.
Choosing the Right Specialist Article
This article defines the QPPV as a system-governance role. Related articles answer narrower questions:
| Reader’s question | Specialist article |
|---|---|
| What are the detailed EU residence, qualification and availability requirements? | EU QPPV Requirements |
| What activities fall within QPPV responsibility? | QPPV Responsibilities |
| How should an organisation select and appoint a QPPV? | Selecting and Appointing a QPPV |
| How should temporary cover operate? | Deputy QPPV |
| What is the PSMF and why does it matter? | What Is a PSMF? |
| How does a person prepare for the career? | How to Become a QPPV |
| How should outsourced activities be governed? | Vendor Oversight |
| How should safety-data exchange with partners be controlled? | What Is an SDEA? |
This separation avoids turning a foundational definition into an abbreviated version of every other QPPV article. It also gives a non-specialist reader a route from the central concept to progressively more detailed subjects.
Review Checklist
When establishing or reviewing a QPPV arrangement, confirm that:
- the individual and the pharmacovigilance system within scope are clearly identified;
- residence and operating-location requirements are met;
- theoretical and practical pharmacovigilance competence is documented;
- medically trained assistance is documented where the legal condition applies;
- role duties and hierarchical relationships are defined;
- authority is supported by real escalation and decision pathways;
- access covers safety, compliance, quality, contractual and organisational information;
- routine reporting and urgent escalation are distinguished;
- product and portfolio information remains current;
- the PSMF accurately describes the role and system;
- delegated tasks and deputy arrangements are controlled;
- 24-hour authority contact is workable and tested;
- important vendor and partner information reaches the QPPV;
- system and portfolio changes trigger QPPV involvement;
- audit findings and corrective actions remain visible through closure;
- and evidence can reconstruct how the QPPV influenced significant decisions.
The checklist represents a practical synthesis of the legal and GVP framework. It is not a substitute for the applicable legislation, current guidance or product-specific obligations.
Key Takeaways
- The QPPV is the continuously available, appropriately qualified individual responsible for establishment and maintenance of the EU pharmacovigilance system.
- The MAH remains the legally accountable entity; appointment or outsourcing does not transfer that responsibility to the QPPV or a service provider.
- QPPV oversight requires visibility, interpretability, influence and closure.
- Product-safety overview is broader than awareness of individual adverse-event reports.
- Authority must work through actual organisational pathways, not merely appear in a job description.
- Permanent and continuous availability is a property of the operating arrangement, supported by continuity and access controls.
- Delegation can distribute tasks, but it must not fragment system or safety-profile overview.
- The PSMF connects the named role to the system it governs and to evidence that the arrangement operates.
- Inspection evidence should show how information became judgement, decision, action and verified outcome.
- Specialist QPPV articles should deepen individual aspects of the role without duplicating this foundational explanation.
References
- European Parliament and Council. Directive 2001/83/EC on the Community code relating to medicinal products for human use, as amended, particularly Articles 8 and 104. urlEUR-Lex — Directive 2001/83/EChttps://eur-lex.europa.eu/eli/dir/2001/83/oj
- European Commission. Commission Implementing Regulation (EU) No 520/2012 on the performance of pharmacovigilance activities, as amended, particularly Article 10. urlEUR-Lex — Implementing Regulation 520/2012https://eur-lex.europa.eu/eli/reg_impl/2012/520/oj
- European Medicines Agency. Guideline on good pharmacovigilance practices: Module I — Pharmacovigilance systems and their quality systems (EMA/541760/2011). urlEMA — GVP Module Ihttps://www.ema.europa.eu/en/documents/scientific-guideline/guideline-good-pharmacovigilance-practices-module-i-pharmacovigilance-systems-and-their-quality-systems_en.pdf
- European Medicines Agency. Guideline on good pharmacovigilance practices: Module II — Pharmacovigilance system master file, Revision 2 (EMA/816573/2011). urlEMA — GVP Module II Rev. 2https://www.ema.europa.eu/en/documents/scientific-guideline/guideline-good-pharmacovigilance-practices-module-ii-pharmacovigilance-system-master-file-rev-2_en.pdf
- European Medicines Agency. Pharmacovigilance system: questions and answers. urlEMA — Pharmacovigilance system questions and answershttps://www.ema.europa.eu/en/human-regulatory-overview/post-authorisation/pharmacovigilance-post-authorisation/pharmacovigilance-system-questions-answers
- European Medicines Agency. Good pharmacovigilance practices, current modules, product- and population-specific considerations and revision information. urlEMA — Good pharmacovigilance practiceshttps://www.ema.europa.eu/en/human-regulatory-overview/post-authorisation/pharmacovigilance-post-authorisation/good-pharmacovigilance-practices-gvp
- European Commission. Commission Implementing Regulation (EU) 2025/1466, amending Implementing Regulation (EU) No 520/2012. urlEUR-Lex — Implementing Regulation 2025/1466https://eur-lex.europa.eu/eli/reg_impl/2025/1466/oj
Regulatory Note
This article explains the EU QPPV framework for professional education. Binding obligations arise from applicable EU legislation and the conditions of individual marketing authorisations. GVP Modules I and II provide regulatory guidance on implementation. Organisational examples, governance questions, analogies and checklist items in this article are explanatory or recommended practice unless directly attributed to a legal requirement.
EMA states that GVP modules are reviewed for revision and that updates are planned following amendments introduced through Commission Implementing Regulation (EU) 2025/1466 and other developments. Readers should therefore verify the current consolidated legislation, current GVP revisions, national requirements and product-specific obligations before applying the article operationally.
The UK operates a related but legally distinct post-Brexit framework. UK QPPV and national-contact requirements should be checked against current MHRA guidance and are addressed separately on QPPV.com.